Kronlein Operation
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The Kronlein operation is a surgical procedure involving the temporary resection of the lateral orbital wall to provide access to the retrobulbar space. First described in 1888, it is used for diagnostic purposes, tumor removal, and treating orbital conditions while preserving the eyeball.
Encyclopedia article (1928–1936)
KRONLEIN OPERATION (Kronlein), proposed by Rudolf Kronlein in 1886 and described by him in 1888, consists of a temporary resection of the outer bony wall of the orbit for the purpose of providing wider access to it. Performed for the first time by Kronlein for the removal of a dermoid cyst of the orbit, it has found application in various cases: for diagnostic purposes in exophthalmos of unknown origin; to facilitate operations in the posterior segment of the eyeball and in the optic nerve (e.g., removal of a subretinal cysticercus, opening of the intervaginal space of the optic nerve in cases of papilledema). It is also used in pulsating exophthalmos for the ligation and removal of pulsating dilated veins and aneurysms; in the removal of optic nerve tumors with preservation of the eyeball; for the removal of orbital tumors in general, especially if they are located deep in the orbit—at its apex, as well as for foreign bodies that have penetrated deep into the orbit or become wedged in its bony walls; sometimes—for finding hidden foci of chronic inflammation, and for the removal of retrobulbar hemorrhages. In all these cases, the primary intention is the preservation of the eyeball and, if possible, the associated soft tissues (nerves, vessels, muscles) necessary for its normal functioning. Technique of the operation. 1. An incision of the soft tissues in the anterior temporal region, arcuate, with the convexity forward, 6–8 cm long. The incision begins above, where the easily palpable linea semicircularis of the frontal bone intersects with a horizontal line passing above the eyebrow parallel to the upper orbital margin, 1–1.5 cm above it. The incision proceeds in an arc downward, and its middle, the most convex part of the arc, is at the outer canthus of the eyelids. From here, the incision goes downward and backward toward the zygomatic arch, where it ends at the midpoint of the straight line connecting the outer angle of the palpebral fissure with the tragus of the auricle. The incision in the upper and lower thirds involves the skin, muscle, and fascia, while in the middle third, it penetrates to the bone at the outer edge of the orbit.
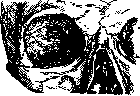
Figure 1. Position and size of the bone wedge.
2. With a sharp elevator, the periosteum (periorbita) is detached on the inner surface of the outer wall of the orbit, starting 1 cm above the sutura zygomatico-frontalis and continuing to the fissura orbitalis inferior. 3. Protecting the soft tissues of the orbit with a wide plate, a resection of the bony wall is performed with a sharp, thin chisel. First, the zygomatic process of the frontal bone is cut at its base; the chisel is then turned, and from the depth of this horizontal section, the outer wall of the orbit is pierced along an oblique line backward and downward to the very inferior orbital fissure at its midpoint. Then, with a lower horizontal section, the frontal process of the zygomatic bone is cut, and continuing this incision, one reaches the beginning of the fissura orbitalis inferior. Thus, the wedge-shaped piece of the outer wall of the orbit is pried out and turned outward (Fig. 1), remaining in connection with the temporal muscle and fascia.
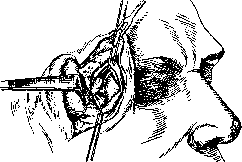
Figure 2. Opening of the retrobulbar space.
4. The exposed periorbita is opened horizontally along the lateral rectus muscle and pushed apart upward and downward; then a wide access to the retrobulbar space is opened for its examination and the application of appropriate surgical procedures, depending on the given case (Fig. 2). To facilitate access to the muscle cone, the lateral rectus muscle is sometimes also cut. Upon completion of the operation in the orbit, this muscle is sutured back, and the bone piece is fitted into its place and secured in its normal position with catgut sutures to the periosteum.
Figure 3. Bone parts, opening even wider access to the orbit.
Finally, the skin wound is sutured. Kronlein himself performed the operation under general anesthesia, but the majority of surgeons use local anesthesia. The operation has received general recognition and wide application in retrobulbar surgery. Damage to the facial nerve and ptosis are observed after it rarely; more often—limitation of the mobility of the lateral rectus muscle. The eyeball is not damaged at all by the operation, and the cosmetic result after it is satisfactory. The Kronlein operation has prompted many modifications, consisting mainly of performing a better incision of the soft tissues [such are the...], and of the bony parts, opening even wider access to the orbit. In general, the original skin incision of Kronlein has not been preserved and has been replaced by ones more convenient in terms of access to the orbit and the integrity of the muscle-fascial structures. The incision of S. S. Golovin (orbitotomia externa simplex) is especially convenient also in that it allows the orbital operation to be started with a simpler technique and only in case of need, after a small additional incision, to proceed to the resection of the outer wall.
Related articles
Cite this page
“Kronlein Operation.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/kronlein-operation/