Kozhevnikov's Epilepsy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the clinical syndrome of Kozhevnikov's epilepsy, characterized by constant clonic muscle twitching interspersed with epileptic seizures. It discusses the historical debate regarding its pathogenesis, specifically whether it originates from cortical motor zone lesions or subcortical structures.
Encyclopedia article (1928–1936)
KOZHEVNIKOV'S EPILEPSY (epilepsia partialis continua, constant partial epilepsy, polyclonia epileptoides continua, Kozhevnikov's clinical form). In 1894, Kozhevnikov described a "special type of cortical epilepsy." Four observations were described, representing a uniform picture of the disease: patients suffered from periodically occurring epileptic seizures, in the intervals between which they had constant clonic convulsions; from these constant convulsions, Jacksonian-type or generalized seizures developed. Consequently, Kozhevnikov's epilepsy represents a special type of epilepsy in which the patient, in the intervals between seizures, has phenomena of constant hyperkinesis of a chronic nature, closely related to the seizures, insofar as the latter develop from them. Kozhevnikov considered it indubitable that the symptom complex he described depends on a lesion of the cerebral cortex in the area of the motor zone or in its vicinity, although in none of his observations was there an autopsy. Therefore, Kozhevnikov proposed the name "epilepsia corticalis, sive partialis continua" for the form he described. N. F. Filatov proposed the name Kozhevnikov's epilepsy, which was preserved and acquired citizenship in foreign literature. Descriptions of observations of Kozhevnikov's epilepsy in the overwhelming majority of cases belong to Russian authors. The picture of constant hyperkinesis in Kozhevnikov's epilepsy bears peculiar features that distinguish it from other forms similar to it in the presence of seizures and by
constant
motor disorders in the interictal period. These features boil down to the following: the clonic nature of the constant contractions, their beginning from a certain territory of muscles and gradual spread to neighboring territories on the same side; the constant participation in the hyperkinesis of the same muscles or muscle groups until new muscles are seized by twitching; the tendency of synergistically working muscles (flexors, extensors) to be involved in constant twitching. In general, the constant hyperkinesis in Kozhevnikov's epilepsy is characterized by conservatism and a very gradual evolution of the picture of constant muscle twitching observed at a given moment, and by the stereotypy or tic-like nature of the latter. If constant twitching tends to vary both in its strength and rhythm, and in its localization in different muscles and even muscle bundles, if they appear on both one and the other side, if they develop and are distributed without any particular order and are generally characterized in all their disorderliness, then in such cases it must be assumed that we are dealing with some other form of constant hyperkinesis in epilepsy, related to Kozhevnikov's, such as: Unverricht's myoclonus epilepsy, Bechterew's choreic epilepsy, prolonged cortical seizures in progressive paralysis of Muratov, paramyoclonus and epilepsy, etc., or with a completely different disease, such as hysteria, athetosis, etc. Insofar as generalized seizures in Kozhevnikov's epilepsy are only of an epileptiform nature, insofar as the very form of epilepsia partialis continua does not always testify to the presence of epilepsy as such in the patient, and insofar as, finally, the picture of constant clonic twitching is in turn diverse, a new term "polyclonia epileptoides continua" has been proposed (Khoroshko) for a group of similar symptom complexes consisting of phenomena of constant clonic hyperkinesis and the presence of epileptoid seizures internally connected with the latter. A tendency toward frequent variation, scattering, and disorderliness of constant twitching is not typical for Kozhevnikov's epilepsy, while the absence of a clonic character in the phenomena of constant hyperkinesis and, consequently, the presence of a tonic or athetoid element in muscle contractions are facts that exclude Kozhevnikov's clinical form. The pathogenesis of Kozhevnikov's epilepsy does not appear to be finally clarified. Kozhevnikov and the overwhelming majority of authors who wrote about this form hold the view that epilepsia partialis continua is a cortical syndrome resulting from one or another lesion of the motor zone of the cerebral cortex. In 1906, a new doctrine about the subcortical origin of the symptom complex of Kozhevnikov's clinical form (Khoroshko) was opposed to this view. It is necessary to note retrospectively that by developing the question of the subcortical pathogenesis of the epilepsia partialis continua syndrome, the question of the role of subcortical mechanisms in the development of phenomena of constant hyperkinesis was raised in Russian literature long before (more than 10 years) the manifestation of increased and even sharpened interest in the pathology and clinic of subcortical formations in Western European neurology. There are still very few pathological-anatomical studies in Kozhevnikov's epilepsy. Microscopic examination of pieces of the cerebral cortex excised during surgical intervention in cases of Kozhevnikov's epilepsy, performed in a few cases, also proved unable to resolve the issue. Alfeevsky, Krumholz, and Omorokov presented anatomical data for the cortical localization of the epilepsia partialis continua symptom complex; Khoroshko published an observation with a lesion of the nuclei lenticularis. In most cases, the pathological-anatomical picture of changes is interpreted by authors as parenchymatous encephalitis, if there are no changes of a special nature (such as, for example, syphilis, progressive paralysis, cysticercus, etc.). The results of surgical intervention in Kozhevnikov's epilepsy are also controversial. There is a whole series of observations where, after the excision of what seemed to be certain areas of the cerebral cortex or their alcoholization, constant convulsions ceased only temporarily, only to reappear after some time. Thus, neither surgical intervention nor anatomical examination has yet provided decisive data for a final judgment on the pathogenesis of Kozhevnikov's epilepsy. Apparently, one must think that the pathogenesis of the epilepsia partialis continua symptom complex can be heterogeneous: in some cases, it depends on diseases of the motor zone of the cerebral cortex, in others—on lesions of subcortical formations. For an intravital conclusion about the pathogenesis, the presence of other symptoms in the given syndrome is of great importance. In the first place here is the presence or absence of disorders of deep sensitivity, the so-called muscle sense (astereognosis). In those cases where deep sensitivity is impaired, there are simultaneously symptoms of a lesion of the motor zone of the cerebral cortex, in particular the posterior central gyrus. Where deep sensitivity is normal, it is permissible to look for and probe for subcortical localization. In cases where an anatomical lesion of the motor zone of the cerebral cortex was proven, signs of a disease of the pyramidal tract (Babinski reflex) were clinically present. Meanwhile, usually in Kozhevnikov's epilepsy, pathognomonic symptoms for pyramidal disease are not noted, and the syndrome itself should be attributed to extrapyramidal symptom complexes, which caused interest in the question of its subcortical localization. Of course, if there are data in the clinical picture indicating damage to the pyramidal tract, then the question of the presence of a lesion of the cerebral cortex is decided positively. With Muratov's syndrome of prolonged cortical seizures, both a disorder of deep sensitivity ("muscle sense") and signs of damage to the pyramidal tracts (pathological reflexes) are usually observed. Based on our schematic representations, it should be considered that the presence of astereognostic-type disorders and deep sensitivity during constant hyperkinesis speaks for a lesion of the posterior central gyrus, and the absence of these disorders in the case of cortical localization of the process—for a lesion of the anterior central gyrus. As for subcortical localization, in Khoroshko's observations, the discussion concerned damage to the nuclei lenticularis, the region of the superior colliculi, and the thalamus as places of presumed topical diagnosis of the Kozhevnikov's epilepsy symptom complex. In two cases, it was possible to establish the transition of the process from the subcortical region to the anterior horns of the spinal cord. Thus, at the present time, the question of the pathogenesis of Kozhevnikov's epilepsy does not appear to be finally resolved; in different cases, in accordance with clinical individual features, one can speak of a different localization of the pathological process. The clinical significance of the Kozhevnikov's epilepsy symptom complex appears to be much more definite and better outlined than the understanding of its pathogenesis.
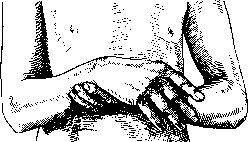
Figure 1. The patient holds the affected hand with the healthy one, in which there are constant twitchings.
K. e.-clinic, symptom complex or syndrome, which may be observed in various diseases: encephalitis, syphilis, traumatic damage, tumors, progressive paralysis, cysticercosis. However, in most cases K. e. occurs as a symptom of subacute or chronic encephalitis. In some cases the disease begins with a seizure, in others with phenomena of constant hyperkinesis. The first seizure occurs sometimes shortly after the first appearance of convulsions or, for example, after 3 weeks, but sometimes only after several years. The same must be said regarding the appearance of constant hyperkinesis following seizures. The frequency of seizures varies greatly: in some cases daily and even several times, in other cases once a year and less often. Seizures are often not entirely typical for an epileptic seizure (partial loss of consciousness, underdevelopment of the seizure, etc.). Phenomena of constant hyperkinesis appear most often on the right side and in the hand (Figure 1), but are also observed in the leg, face, tongue, palate, pharynx, larynx, etc. Constant hyperkinesis is sometimes observed on both sides of the body. In the hand three types of constant twitching are observed: flexor (most often) (Figure 2), extensor (Figure 3), mixed (Figure 4 and 5). The strength of muscular contractions varies greatly; patients have 'light' and 'heavy' days. Various psychological moments intensify the phenomena of constant hyperkinesis. In sleep, twitching is absent in some patients, while in others it does not cease. Before a seizure, there is usually an intensification of constant muscular contractions, after a seizure, a weakening of them. Often after a seizure, twitching appears in muscles not previously affected by the last seizure. Minor named the constant twitching in K. e. 'aura continua', emphasizing thereby the internal connection between seizures and hyperkinesis. There is a series of transitional cases from K. e. to other border forms and combinations: tic+epilepsia, chorea+epilepsia, or epilepsia choreica, paramyoclonus+epilepsia, myoclonia+epilepsia, tremor+epilepsia, athetosis+epilepsia, etc. In addition, in the differential-diagnostic respect one should bear in mind the possibility of development of a similar symptom complex in hysteria, multiple sclerosis. It is especially necessary to note that in K. e. there is an internal connection between seizures and constant hyperkinesis, while there are frequent cases when we have only an external combination of epilepsy with some phenomena of hyperkinesis.
Figure 3. 'Finger' position. Figure 3. Extensor type of constant hyperkinesis of the hand. (Figure 3).
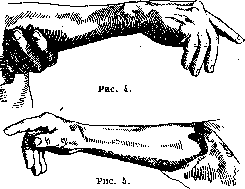
Figure 4 and 5. Mixed type of constant hyperkinesis of the hand.
Kozhevnikov's epilepsy stands apart from the observations of Omorokov, made in Siberia. The author is inclined to consider that among the Siberian, especially the peasant population of forested areas, K. e. occurs very frequently. He believes that in most cases this is an infectious disease of the encephalitis type with sharply expressed parenchymatous changes on the part of nerve cells and interstitial substance. The author describes in the nerve cells of the cerebral cortex peculiar inclusions, which he considers as a product of the tissue reaction to an unknown pathogen, analogous to Negri bodies in rabies. Omorokov counts 42 cases of K. e. described in the literature, while through his clinic in Tomsk passed 52 cases over 8 years. It is well known that in Siberia various diseases with phenomena of convulsive twitching are very widespread. On the other hand, it is necessary to remember that in combination with epileptic seizures the most diverse manifestations of constant hyperkinesis can occur. The course of the symptom complex of K. e. is usually chronic. The disease is extremely stubborn and resists various measures, if it is not possible to successfully conduct therapy eliminating its cause. Bromides, luminal are of little effect, especially regarding constant hyperkinesis. In recent times some improvement of the disease phenomena could be noted after the application of oxygen therapy and roentgen therapy to the subcortical nodes. Surgical intervention on the cerebral cortex and its membranes, as has been said, is far from always accompanied by a lasting success and does not always pass without recurrence; sometimes the operation leads, due to the formation of new scars, to a certain deterioration in the patient's condition. However, a number of authors describe good results of surgical intervention. A milder intervention than the removal of pieces of cerebral cortex with suspected areas of brain substance of the motor zone is the introduction of alcohol into the brain substance proposed by Razumovsky. For those who share the views on the subcortical pathogenesis of Kozhevnikov's epilepsy, the alcoholization of peripheral nerve trunks with the aim of stopping the conduction of irritating impulses to their constant contraction is more acceptable. Alcoholization peripherally practically gives certain results. Where the question of reflex pathogenesis of the disorder arises, interventions for cutting off irritating reflex influences from the periphery are indicated.
Related articles
Mentioned in
Cite this page
“Kozhevnikov's Epilepsy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/kozhevnikovs-epilepsy/