Extrasystole
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article defines extrasystole as a form of cardiac arrhythmia characterized by premature contractions of the heart or its parts, typically originating from heterotopic impulses rather than the sinus node. It discusses the historical understanding, experimental induction methods, etiology, and the distinction between organic and functional (neurotic) causes.
Encyclopedia article (1928–1936)
EXTRASYSTOLE (from Latin extra—outside and Greek systole—contraction), extrasystolic arrhythmia, represents one of the forms of cardiac rhythm irregularities, in which the normal mechanism is disrupted by premature additional contractions of the entire heart or its individual parts.
Extrasystole is caused by abnormal excitations, generated almost always not in the highest regulatory center—the sinus node—but in other areas of the myocardium, i.e., by heterotopic impulses. However, in rare cases, the additional excitation can apparently also arise in the Keith-Flack node (sinus extrasystole). Usually, one encounters extrasystoles originating from some area of the atrial musculature (auricular extrasystoles) or ventricles (ventricular extrasystoles), and much more rarely from the Aschoff-Tawara node (atrioventricular extrasystoles).
Extrasystoles for the most part appear in the form of single premature beats, arising at the most diverse intervals, or they exhibit a tendency toward a regular return, i.e., they repeat after a certain interval (allorhythmia); they can also appear in groups (accumulated extrasystoles). Depending on the sequence and frequency, extrasystoles disrupt the basic sinus rhythm to varying degrees. As one of the clear, easily detectable objective signs of cardiac activity disorder, extrasystoles, like other arrhythmias, were noted back in antiquity. Already among the ancients, we find such names as pulsus deficiens, intermittens, etc.
Since then, until almost the end of the 19th century, the study of arrhythmias advanced very little. Their origin remained completely obscure, and classification was conducted according to purely external signs. Thus, as late as 1876, Riegel divided arrhythmias into only 2 groups: allorhythmias and arrhythmias of the irregular type. The study of individual myocardial functions in the light of Engelmann's myogenic theory and the introduction of precise graphic methods of investigation produced a revolution in views on arrhythmias in general and extrasystoles in particular. Of the various methods of investigation, electrocardiography proved to be the most fruitful, since with its help it is possible to analyze with the greatest simplicity, accuracy, and clarity all those variations of extrasystoles that are encountered in pathology.
Experimental data are important for clarifying the origin of arrhythmia. The experiments of Marey, Engelmann, Cushny, and others on the hearts of cold-blooded and warm-blooded animals clearly showed the conditions for the appearance of premature contractions. During diastole, upon the conclusion of the refractory phase, it is easy to induce extrasystoles by the most diverse influences: mechanical (pricking with a pin, touch, compression of the heart), electrical (discharge of an induction current), thermal (rapid local increase in temperature), and chemical (crystal of salt, drop of acid). A whole series of poisons also causes extrasystoles (preparations of the digitalis group, strophanthin, adrenaline, thyreoidin, caffeine, nicotine, strychnine, physostigmine, muscarine, calcium, barium, preparations of salicylic acid, etc.). Extrasystoles also arise during a sharp increase in pressure in the left ventricle (during compression of the aorta) or in the right (during clamping of the pulmonary artery). Disturbances in myocardial blood supply have the same effect; thus, upon ligation of a branch of the coronary artery, extrasystoles appear, at first single, then grouped, often originating from different areas, then (if a sufficiently large branch is ligated)—extrasystolic tachycardia and finally ventricular fibrillation. The same sequence is observed during poisoning with large doses of strophanthin. Irritation of extracardiac nerves, for example, combined irritation of the vagi and sympathici or even one of them after the preliminary introduction of known poisons that increase the excitability of lower centers, can also cause extrasystolic arrhythmia.
Etiology. Pathogenesis. Extrasystole is one of the most frequent rhythm disorders and is observed at all ages in both men and women. In childhood, however, it is a rarity and usually appears after acute infectious diseases, such as acute rheumatism, diphtheria, severe tonsillitis, typhus, scarlet fever, etc. Most often, extrasystoles are encountered in elderly persons. According to Mackenzie, they can be found upon frequent examination in every practically healthy person over the age of 60. In clinical material, organic diseases of the cardiovascular system predominate: mitral and aortic defects, muscular lesions of the heart, cardio-arteriosclerosis, and hypertension. However, according to Wenckebach and Winterberg, among patients with extrasystoles, only 8% had elevated blood pressure, and among hypertensives, only 11% suffered from extrasystoles, and moreover, equally often in both moderate and significant hypertension. Extrasystole can be a consequence of reflex influences in various diseases, mainly of the abdominal cavity organs (in cholecystitis, appendicitis, digestive disorders with abdominal bloating and displacement of the diaphragm upward, etc.). Among toxic influences, hyperthyroidism is significant, as well as various poisons, especially digitalis preparations in large doses (see below), nicotine, etc.
There is no doubt that along with the indicated pathological conditions, extrasystole is often encountered in healthy individuals as well. Many cases have been described, followed over the course of decades, in which there were not only no clear signs of organic heart suffering but also no symptoms of circulatory insufficiency. These are the cases in which the arrhythmia is linked to a functional disorder of the nervous system and is considered a sign of cardiac neurosis or is distinguished as an independent form of localized neurosis under the name "essential extrasystole" (Romberg). The role of neuropsychic factors in the etiology of extrasystole is undoubtedly great, but it is not uniform in different cases. Some patients become neurasthenics as a result of their arrhythmia (here the influence of the physician is of great importance, whose words can turn into a psychic trauma—iatrogenic psychoneurosis), others suffer from extrasystoles on the basis of their inherent constitutional peculiarities of the psyche and the autonomic nervous system. However, in many cases of vegetative neurosis with extrasystoles, one can still find in the anamnesis indications of a series of past infections or cardiac overstrain, and therefore it is difficult to exclude the possibility of subtle organic changes in the myocardium, undetectable by modern methods of investigation. The mechanism of the origin of spontaneous extrasystoles can be imagined in such a way that heterotopic impulses are formed as a result of an increase in the automatism of the lower centers, i.e., an increase in the ability of various sections of the specific muscular system to generate excitations independently. The conditions contributing to the awakening of automatism are: 1) an increase in the excitability of these centers and 2) a decrease in the function of the sinus node. Often both factors are combined. Thus, digitalis increases the tone of the n. vagus, thereby inhibiting the function of the sinus node and atrioventricular conduction, and at the same time increases the automatism of the lower centers. According to Lewis, the impulses causing extrasystoles differ from normal ones not only in the place and time of origin but also qualitatively: in other words, they are heterogenetic in contrast to physiological homogenetic impulses. However, this point of view remains controversial. Between both types, there is a whole gamut of transitions; there are apparently no fundamental differences here.
9 § is: Figure 1. Dissociation with interference. The atria and ventricles contract independently of each other (dissociation), with the former being subject to the sinus node and the latter to the Tawara node. The ventricular rhythm is somewhat faster than the atrial rhythm. Individual sinus impulses (2,6) that coincide with the excitable phase of the ventricles cause their premature contraction (interference) and thus shift the automatic ventricular rhythm. In some cases, E. may arise due to the constant work of a second center, as demonstrated by the Vienna authors Kaufmann and Rothberger. Based on a thorough analysis of a series of cases of extrasystolic arrhythmias, mainly of the allorhythmic type, they believe that the existence of two interfering rhythms in the heart is possible, i.e., along with sinus impulses, excitations can rhythmically arise in a new pathologically altered site. They call this additional rhythm 'pararrhythm,' and the irregularity of cardiac activity that results from the functioning of a new center along with the higher one—'parasystole.' A double rhythm can exist only on the condition that each center is protected from external irritations and can work unimpeded. In the opposite case, the sinus node would have to suppress the pathological source of impulses, as happens in normal conditions, or the lower center, having a higher frequency, would become dominant, as in paroxysmal tachycardia, and would displace the normal rhythm. Consequently, the rhythmic work of two centers is possible only in the presence of a 'protective block' around the site of impulse origin. In addition, since only part of the pathological impulses pass to the myocardium, it is obvious that part of them are delayed ('variable block on exit'). The complexity of these assumptions naturally raises objections. Attempts have been made to identify simpler forms of parasystole. Cases have been described that do not require the assumption of 'block on exit,' such as 'dissociation with interference' (Mobitz et al.) (fig. 1) and 'parasystole with simple interference' (Singer, Winterberg). In all the mentioned cases, the proof of pararrhythm is the regular relationships between the intervals separating the extrasystoles (these intervals must be a multiple of a known magnitude—the pararrhythmic period). However, if this magnitude is very small (e.g., less than 0.30 sec), then the calculation becomes very shaky. Moreover, it is unprovable in cases where E. appear strictly regularly at equal time intervals after normal beats. Here heterotopic impulses are closely connected with nomotopic ones. It is clear, for example, that in persistent bigeminy with such a connection, the distances between extrasystoles will be the same, provided the sinus rhythm is regular. In such cases, there is no reason to speak of parasystole; one must assume that the normal impulse somehow causes additional excitation. The mechanism of the occurrence of these irregularities is explained by the theory of 're-entrant waves' (Lewis), based on the experiments of Mines and de Boer. With deterioration of exchange in the cardiac muscle and unevenness of the refractory period in different parts of the myocardium, a single excitation can proceed in stages and make several circular movements, causing two or more systoles. Thus, the mechanism of multiple E., paroxysmal tachycardia, flutter, and fibrillation approaches each other (see Atrial fibrillation). In conclusion, it should be said that the pathogenesis of E. in different cases is apparently different, and that systematic studies of recent years have significantly deepened our understanding of the mechanism of occurrence of various types of this arrhythmia. Symptomatology. Graphic data. Of all disorders of cardiac rhythm, E. belongs to those that most often cause unpleasant subjective sensations. The complaints of patients are very diverse and variable in nature and intensity, ranging from mild, indefinite sensations of palpitations or cardiac arrest to distressing constrictions, blows, and pains in the heart area, radiating to the neck, shoulder, arm, etc. All these phenomena occur in some patients during physical exertion, excitement, or after a heavy meal, while in others—and this is characteristic of E.—at rest, after work, in the evening. Quite often they appear in bed, when falling asleep, and cause the patient to jump up and fear sleep. Sometimes E. are observed only in a certain position (lying, sitting). Whether these phenomena should be attributed exclusively to E. in each individual case is still a question. With careful observation, it can be easily established that in the same patient, E. sometimes causes unpleasant sensations and sometimes passes unnoticed. Obviously, other factors play an important role, such as the state of the psyche and the autonomic nervous system, strengthening or weakening of cardiac activity, vasoconstrictor phenomena, changes in blood pressure, the height of the diaphragm, etc. It is noted that subjective sensations in E. are observed much more often in functional than in organic heart diseases, and that people engaged in intense mental work and leading a restless lifestyle often suffer (in particular, a relatively high percentage of doctors, according to Mandelstam—9%). Sometimes the described typical complaints, associated with arrhythmia, constitute the main or only content of the patient's history, and in the absence of visible damage to the cardiovascular system or with complete compensation of the underlying disease, E. acquires the character of an independent clinical syndrome ('essential E.'). In other cases, arrhythmia does not cause special sensations and is discovered only by chance. Objectively, the recognition of single extrasystoles in most cases is not difficult, both on palpation of the pulse and especially on auscultation of the heart. Against the background of a correct rhythm, a weak premature pulse wave (break) is determined. It can be so weak that it does not reach the periphery (pulse deficit) or at least is not captured on palpation and can be registered only on a sphygmogram. On auscultation, the premature beat corresponds to two additional tones, of which the first is louder than usual, sometimes clapping, and the second is weakened. In very early extrasystoles, the pressure in the left ventricle sometimes increases so insignificantly that it is unable to open the aortic valves (sterile extrasystoles). In this case, only one premature additional tone is heard. If there are noises in the heart, then with premature contractions they may change in strength and in different ways: the systolic noise becomes weaker, the diastolic-presystolic sometimes strengthens, and sometimes weakens. For ventricular extrasystoles, the presence of a compensatory pause and consequently the preservation of the basic rhythm is characteristic. Ventricular extrasystoles do not pass to the atria and do not interfere with their rhythmic contractions. However, the next sinus impulse coming from the atria to the ventricles is absent, as it finds the ventricular muscle in an inexcitable phase (in extrasystole). Only the next impulse passes unimpeded to the ventricles and causes their normal contraction. Due to this, a compensatory pause follows the premature contraction, and the sum of the distances from the normal wave to the extrasystole and from the extrasystole to the next normal wave equals twice the normal cardiac period. For auricular and atrioventricular E., the compensatory pause is shortened or even equals the usual sinus period (in sinus E.). For ventricular and atrioventricular E., another phenomenon is characteristic. During premature contraction of the ventricles, the atria are unable to empty their contents in the usual direction, but drive blood back into the veins. The consequence of the simultaneous systole of the atria and ventricles is a sudden, sharp swelling of the neck veins, visible to the eye and giving a high wave on the phlebogram. For the exact determination of the varieties of E., however, graphic methods must be used, preferably electrocardiography. When analyzing the phlebogram, it is necessary first to recognize the waves of the normal venous pulse, and then establish whether the premature contraction begins with the ventricular wave s. If so, the extrasystole is ventricular; otherwise, it arises in the atrium. For ventricular and atrioventricular E., a large a+c wave is visible on the venous curve, which follows the v wave of the previous contraction or merges with it, and for ventricular extrasystoles, the preservation of the atrial basic rhythm is characteristic. In general, the changes in the venous pulse are diverse depending on the place and time of origin of the extrasystole. It is easier to analyze the nature of the arrhythmia on the electrocardiogram (see the scheme of E. in the article Heart arrhythmia). Auricular E. differ, besides their prematurity, by an atypical (in form and size) P wave and a normal ventricular complex.
When R appears very early, it can be superimposed on the preceding T wave (Fig. 2); sometimes an additional auricular extrasystole occurs. The impulse encounters non-excitable tissue and cannot pass to the ventricles; then one speaks of a blocked extrasystole. Sinus extrasystoles do not differ in form on the electrocardiogram from normal beats. In rare cases, with very early excitations and incomplete restoration of conductivity in the ventricles, the ventricular complex of an auricular extrasystole is atypical and resembles a ventricular extrasystole, from which it differs, however, by the presence of a preceding P wave. In atrioventricular dissociation, the atria and ventricles contract almost simultaneously, since the impulse, originating from the Tawara node, spreads to both sections. On the electrocardiogram, the P wave is negative (Fig. 3) and approaches or merges with the ventricular complex, disappearing within it; the latter has the usual supraventricular form. Ventricular extrasystoles, which occur more frequently than others, give particularly characteristic and distinctive electrocardiograms. They differ, besides their prematurity and absence of a P wave, by their considerable size and atypical form of the ventricular complex (Figs. 4, 5, 6 and 7). The two main types of ventricular extrasystoles (Figs. 4 and 5) are very similar to the dextro- and levogram obtained by cutting the right or left leg of the His bundle. The first consists of a high sharp wave directed upward and a wide gentle wave directed downward (the right-sided type is characteristic of extrasystoles originating from the right ventricle); the second has the reverse form (the left-sided type-in extrasystoles of the left ventricle). The question of the connection between the type of electrocardiogram and the localization of the impulse in one or the other ventricle, however, proved to be more complex than it seemed at first on the basis of experimental data. Irritation of various areas of the myocardium gives various variations of the indicated basic types of electrocardiogram. Furthermore, the form of the electrocardiogram in many cases changes sharply in different leads. Thus, in lead I an extrasystole may have the appearance of a left-sided type, while in leads II and III it may be right-sided and vice versa (discordant type-Fig. 4). At present, it is believed that for determining the place of origin of ventricular extrasystoles, their form in lead III is of greater importance. Therefore, the extrasystole depicted in Fig. 4 should be considered a right-sided, and in Fig. 5 a left-sided ventricular extrasystole. But with respect to the human heart, even this position cannot be considered firmly established. The advantage of the electrocardiogram is also that from the curve it can be seen whether all extrasystoles originate from one place or from different places; polymorphism of extrasystoles indicates polytopic origin of impulses. The magnitude of the waves of the electrocardiogram does not correspond to the force of heart contraction. - In some
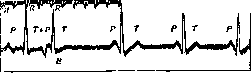
Figure 3. Atrioventricular extrasystole with inverted P wave (E).
electrocardiograms. They differ besides prematurity and absence of a P wave by their considerable size and atypical form of the ventricular complex (Figs. 4, 5, 6 and 7). Two main types of ventricular extrasystoles (Figs. 4 and 5) are very similar to the dextro- and levogram obtained by cutting the right or left leg of the His bundle. The first represents a high sharp wave directed upward and a wide gentle wave directed downward (the right-sided type is characteristic of extrasystoles originating from the right ventricle); the second has the reverse form (the left-sided type-in extrasystoles of the left ventricle). The question of the connection between the type of electrocardiogram and the localization of the impulse in one or the other ventricle however proved to be more complex than it seemed at first on the basis of experimental data. Irritation of various areas of the myocardium gives various variations of the indicated basic types of electrocardiogram. Furthermore the form of the electrocardiogram in many cases sharply changes in different leads. Thus in I lead an extrasystole may have the appearance of a left-sided type while in II and III - right-sided and vice versa (discordant type-Fig. 4). At present it is believed that for determining the place of origin of ventricular extrasystoles their form in III lead is of greater importance. Therefore the extrasystole depicted in Fig. 4 should be considered right-sided and in Fig. 5 left-sided ventricular extrasystole. But with respect to the human heart and this position cannot be considered firmly established. The advantage of the electrocardiogram consists still in that from the curve it is visible whether all extrasystoles originate from one place or from different; polymorphism of extrasystoles indicates polytopic origin of impulses. The magnitude of the waves of the electrocardiogram does not correspond to the force of contraction of the heart. - In some
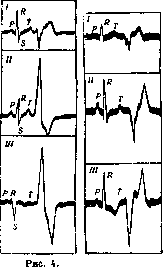
Figure 5.
Figure 4. Ventricular extrasystoles of discordant type; shown is an extrasystole originating from the right ventricle (right-sided type in II and III leads but left-sided type in I lead). Figure 8. Ventricular extrasystoles of concordant type; shown is an extrasystole of the left ventricle giving an atypical form of electrocardiogram of left-sided type in all leads. cases mainly with slow sinus rhythm ventricular extrasystoles do not displace the following normal contraction but end before its appearance (interpolated or interpolated extrasystoles Fig. 6). Such extrasystoles are separated from the subsequent regular contraction not by a compensatory pause but by a shortened interval. Their recognition on the electrocardiogram presents no difficulties. Usually they lengthen the P-R interval of the following systole because the conductivity of the atrioventricular bundle does not have time to completely restore by this time. Early ventricular extrasystoles in rare cases
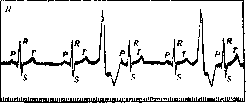
Figure 6. Two interpolated extrasystoles.
can apparently pass in the reverse direction along the His bundle and cause contraction of the atria before the normal systole occurs. Such "reverse" retrograde extrasystoles have been firmly established only experimentally. Allorhythmias are those irregularities of rhythm in which the disorder of the normal mechanism itself repeats with a certain regularity (see Heart arrhythmias). The most frequent and simple form is bigeminy (see) in which each normal beat is accompanied by an extrasystole originating more often from the ventricles less often from the atria (Fig. 7). In other cases one sinus excitation and two extrasystolic excitations alternate regularly (pulsus trigeminus) or one
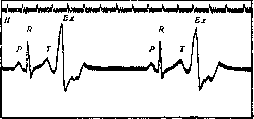
Figure 7. Ventricular extrasystoles of right-sided type with compensatory pause.
sinus and three extrasystolic (pulsus quadrigeminus) etc. More complex allorhythmias are also observed in which whole series of normal and heterotopic excitations alternate in a certain sequence. Such cases represent a transition to paroxysmal tachycardia and are distinguished by the high frequency of the extrasystolic rhythm giving bursts of tachycardia (tachycardie en salves of French authors). Of all allorhythmias bigeminy is practically important. On the pulse curve it gives the regular alternation of a large and small wave the small wave being premature. In this way pulsus bigeminus differs from pulsus alternans. If however extrasystoles appear late the difference is less clear. An apparent bigeminy occurs in the case if every third beat is missing due to partial atrioventricular or sinoauricular dissociation or due to the fact that after two sinus impulses a very early unproductive extrasystole appears. However in this case the paired waves of the arterial pulse are equal in magnitude. The nature of allorhythmia is even easier to recognize from the electrocardiogram. Often pulsus bigeminus simulates bradycardia since the waves of the extrasystole do not reach the periphery-bradysphygmia. On auscultation of the heart palpation of the apical impulse as well as on recording of curves it is easy to ascertain the true character of cardiac activity. Bigeminy can be prolonged or transient often it recurs giving way at times to a normal rhythm tachycardia or chaotically occurring extrasystoles. It is well known that bigeminy appears due to ventricular extrasystoles under the influence of digitalis preparations. In some patients allorhythmia appears with excessive doses or too prolonged treatment; in others with more severe heart damage already after a short time. Generally bigeminy appearing during prolonged treatment is a symptom of intoxication and is an indication to discontinue the drug. It indicates severe damage to the myocardium (Gallavarden's "symptom of alarm"). Extrasystoles can be combined with all other types of arrhythmias most often with sinus and fibrillation. Sinus bradycardia arrhythmia and extrasystoles often occur together which indicates the influence of the vagus nerve (direct or reflex) in the occurrence of these disorders of cardiac activity. In such cases turning off the endings of the n. vagi with the help of atropine can temporarily eliminate the abnormal mechanism. The same result is often obtained with physical exertion (test with movement) or with inhalation of amyl nitrite. On the contrary by reflex irritation of the n. vagi (for example carotid or ocular reflex) in a number of cases it is possible to cause extrasystoles. The combination of extrasystoles with fibrillation is common especially during treatment with digitalis (in approximately */3 of all cases of fibrillation). These are ventricular extrasystoles but they are not accompanied by a compensatory pause due to the absence of sinus rhythm. With more marked increase and irregularity of ventricular activity they can be recognized only on the electrocardiogram.-Close to extrasystoles are heterotopic beats which do not arise on the basis of increased excitability of the cardiac muscle but due to decreased activity of the higher center. They represent manifestations of a slowly and rhythmically working secondary or tertiary center. Individual impulses often occur at the end of long pauses (in sinus bradyarrhythmia) as "escaped beats" (Lewis escaped beats passive heterotopic contractions Wenckebach-Fig. 8) replacing the missing normal excitations (see also Heart arrhythmias). In the case if the sinus node ceases to function
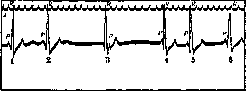
Figure 8. Sinus bradyarrhythmia. "Escaped beats" (.3,4).
to inhibit (in inflammatory changes, sclerosis of vessels or under the influence of the vagus nerve), then the Tawara node can become the leading center and a nodal rhythm is established (nodal rhythm McKenzie). The atria and ventricles contract simultaneously or almost simultaneously (fig. 1). The frequency of the rhythm does not exceed 40-50 beats per minute. The form of the complexes on the electrocardiogram is the same as in atrioventricular extrasystoles (fig. 1 and 8). If, however, the sinus node and a heterotopic (atrioventricular or ventricular) automatic center work with almost the same frequency, then the leading role can repeatedly pass from one to the other and interference of two rhythms occurs (see above). Diagnosis. The clinical picture and the electrocardiogram have great importance. Prognosis. In many cases, the characteristic complaints make it possible to make a presumptive diagnosis based on the history. Extrasystoles can be distinguished from other arrhythmias in most cases already during the direct examination of the patient, best of all during auscultation of the heart. Both single extrasystoles and simple arrhythmias give very characteristic sound phenomena. Palpation of the pulse alone is not sufficient, since the omission of individual pulse beats can be caused by other disorders of the cardiac mechanism (marked sinus arrhythmia, incomplete block). Difficulties arise with very frequent grouped extrasystoles and with extrasystolic tachycardia; here the distinction from paroxysmal atrial fibrillation or sinus arrhythmia without graphic methods (electrocardiogram) is often impossible. Extrasystoles in themselves are not a severe disorder of rhythm and do not have a special effect on the circulation. The presence of extrasystoles, however, necessitates a thorough investigation to determine their cause. If there are no symptoms of organic disease and functional insufficiency of the heart, then the extrasystoles should not be given great importance; practically the heart can be healthy. In any case, the presence of only extrasystoles does not give the right to speak of heart disease and is not a symptom that allows one to distinguish organic disease from functional. In a number of cases, however, extrasystoles acquire the significance of a symptom of damage to the heart muscle or a precursor of circulatory disorders. Thus, during or after an acute infectious disease, extrasystoles, especially with a frequent pulse, indicate pathological changes. Numerous extrasystoles from different foci (polymorphic), differing on the electrocardiogram by their polymorphism, are observed in severe widespread changes in the myocardium. More frequent atrial extrasystoles in mitral stenosis and cardiosclerosis may be a precursor of fibrillation. In hypertension and aortic insufficiency, left ventricular extrasystoles are often a symptom of the beginning weakness of the heart. An unfavorable prognostic significance has digitalis bigeminy, as was said above. Accumulated extrasystoles, forming sometimes attacks of tachycardia, by no means always indicate organic heart disease, and all the more the onset of decompensation. There is no essential difference between atrial and ventricular extrasystoles, although the former are more often observed in functional heart diseases. In general, a correct evaluation of extrasystoles is possible only in connection with the data of the history and a complete objective investigation taking into account socio-domestic and production factors; in individual cases it is necessary to repeat the investigation after certain intervals. Treatment. In the first place stands the treatment of the underlying disease. In the presence of organic heart disease, extrasystoles rarely require special attention. As a rule, extrasystoles must be considered a contraindication to the prescription of digitalis; only in the case if ventricular extrasystoles are accompanied by tachycardia and signs of the onset of heart failure, they cannot be considered a contraindication to the prescription of digitalis, on the contrary, under these conditions the irregularity of the rhythm often disappears with the improvement of the circulation under the influence of digitalis. In any case, extrasystoles or especially bigeminy, appearing during treatment with preparations of the digitalis group, are a symptom of intoxication and an indication to discontinue these remedies. If extrasystoles are the result of reflex or toxic influences, then the elimination of the cause is important (treatment of diseases of the abdominal organs, especially constipation, stomach distension, bloating, etc., restriction of smoking, alcohol, coffee, etc.). In so-called essential extrasystoles, mental calm of the patient and treatment of the nervous system are important (explanation to the patient of the non-seriousness of the suffering, regulation of the way of life, elimination of overwork, rest, light hydrotherapy, nervina, sedativa). If these means are insufficient, quinine recommended by Wenckebach can be prescribed, which has a pronounced ability to reduce the excitability of the heart muscle. The usual course: 3 times a day 0.1-0.2 of any quinine preparation for 10 days with a subsequent break of 8-10 days. For persistent accumulated extrasystoles, quinidine can also be tried in small doses - 0.2-0.3 once or twice a day as needed. Among other means, strychnine and theobromine can be mentioned, which are often combined with quinine in the form of pills. Atropine often eliminates extrasystoles, but mostly only for a short time. In general, we have a whole series of effective remedies (see Heart Arrhythmias), but to judge the therapeutic effect of individual means is usually not easy due to the variability and inconstancy of the arrhythmia. If the extrasystoles do not cause special disorders, then the indicated treatment may be superfluous and it is sufficient for the patient to be explained that the arrhythmia should not inspire fears.
IV. Mandelstam.
Related articles
Mentioned in
Cite this page
“Extrasystole.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/extrasystole/