Coloboma
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia defines coloboma as a congenital or acquired defect in the eye's structures. It details the clinical presentation, anatomical variations, and hereditary nature of colobomas affecting the eyelids, iris, ciliary body, choroid, retina, optic nerve, lens, and vitreous body.
Encyclopedia article (1928–1936)
COLOBOMA, coloboma (from the Greek kolo-bos—mutilated), a defect in the membranes of the eye, either acquired or congenital (genotypic). Acquired colobomas occur sometimes due to trauma, but most often after surgeries (coloboma of the iris). Colobomas of the eyelids, iris, ciliary body, choroid, retina, optic nerve, lens, Zinn's zonule, and vitreous body have been described. A coloboma of the eyelid (Figure 1) represents a limited defect, usually triangular, less often quadrilateral in shape, with the base at the edge of the eyelid and the apex at the orbital margin. The size of the coloboma varies from a small notch to a complete splitting of the entire eyelid. Colobomas can be on one or several eyelids; there may be several colobomas on one eyelid. There is no typical location for a coloboma, but they are often situated in the middle of the eyelid; their edges are straight or serrated. Eyelashes and Meibomian glands are absent at the site of the coloboma. Sometimes a bridge of skin stretches from the upper edge of the coloboma, fusing with the cornea. Often, dermoids are found on the edges of the coloboma, and on the eyes themselves—corneal opacities, coloboma of the iris, microphthalmia, and other defects. On the body—harelip, cleft palate, etc.—Coloboma of the iris (Figure 2)—a defect in the iris in the form of an isosceles triangle with slightly curved edges and an apex at the ciliary margin, capturing from 1/8 to the entire volume of it. There can also be rudimentary colobomas in the form of small notches on
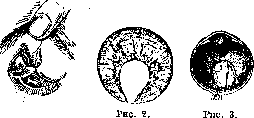
Figure 1.
the edge of the pupil, in the form of a thinning of the iris stroma, and in the form of pigment-free or, conversely, more pigmented stripes. Sometimes the area of the coloboma is divided by a horizontal bridge of preserved tissue. Along the edges of the coloboma, for some distance, one can trace the sphincter of the iris, which is a distinguishing feature of hereditary colobomas from acquired colobomas. The typical position of a coloboma is directly downward or downward-inward, but there are also atypical colobomas located in other directions, most often outward. Colobomas are more often found in one eye, but can be in both. Very often, other anomalies are simultaneously present in the eyes. Coloboma of the ciliary body can occur both on its own and in connection with coloboma of the iris and choroid (Figure 3), forming a cleft, usually directed downward, or in a rudimentary form in the form of pigmented or pigment-free stripes. Colobomas of the ciliary body are difficult to diagnose clinically. The ciliary muscle may remain intact even with a clearly expressed coloboma of the ciliary body. In some breeds of chickens (Cochin), colobomas of the ciliary body are regularly present. Coloboma of the choroid is detected by ophthalmoscopy in the form of a white, sharply defined area, clearly standing out against the red background of the fundus (Figure 4), and its edges are often bordered by pigment. The vessels of the choroid are absent in this area; the vessels of the retina run along the edges of the coloboma or around it; the vessels of the sclera present on the coloboma are often tortuous. Sometimes colobomas reveal a difference in level compared to the rest of the fundus, bulging backward in whole or in part. Sometimes a semblance of a seam in the form of a cord is noted along the midline of the coloboma. The shape and size of the coloboma vary; sometimes colobomas occupy the entire extent from the optic disc, capturing the latter to the very periphery of the fundus. The typical position of the coloboma is downward, corresponding to the location of the embryonic fissure of the optic vesicle (Figures 5 and 6), but there are

Figure 4.
atypical colobomas located in other directions. Among such colobomas is the coloboma of the macula, located outward from the optic disc and, in its ophthalmoscopic picture, completely resembling a coloboma of the choroid. Upon anatomical examination, in individual cases, a preserved retina was found at the site of the coloboma; but most often the area of the coloboma is occupied by connective tissue. Thus, it is very often necessary to speak not only of a coloboma of the choroid, but also of a coloboma of the retina. With a coloboma, there is a corresponding defect in the visual field; in addition, visual acuity is usually reduced due to the general underdevelopment of the entire eye. Simultaneously with coloboma of the choroid or separately from them, colobomas of the optic nerve are observed (Figure 4), with a depression in the form of a pit found in the lower part of the disc, or the entire disc is increased in volume and deepened. The central vessels of the retina in this case no longer exit from the middle of the disc, but appear either from below, or from above, or along the entire periphery of the depression. If there is no microphthalmia simultaneously, then myopia is noted. A common phenomenon is a decrease in visual acuity and a defect in the visual field. Congenital changes in the form of a crescent or cone downward from the optic disc, often accompanied by amblyopia, should also be considered as a rudimentary coloboma of the optic nerve. With a coloboma of the lens, there are depressions of various sizes and shapes on its edge, visible either through the coloboma of the iris or with a dilated pupil. Sometimes, instead of depressions, there are only, as it were, rectilinear cut edges of the lens in limited places. The third type of coloboma of the lens, according to Hippel, consists in the fact that the lens tapers downward and lengthens, with its anteroposterior diameter decreasing. In most cases, colobomas are directed downward, but can be in other directions. Often, colobomas of the iris, choroid, and optic nerve are present simultaneously. Various forms of lens opacity are not uncommon with colobomas. Defects or colobomas of Zinn's zonule are observed with coloboma of the lens and coloboma of the ciliary body. Their shape is triangular with the apex at the edge of the lens. A coloboma of the vitreous body represents a defect in its lower part or along its entire length from the optic disc to the ciliary body, or only in the anterior or posterior segment. The height of this defect varies, and it is filled with connective tissue cords containing vessels, which penetrate into the eye from the disc or from below. Primarily, a coloboma exists in the walls of the optic vesicle, i.e., in the retina and pigment epithelium developing from them, and only subsequently does the choroid take part in this. Therefore, according to the fair remark of Hippel, the usual expression "coloboma of the choroid" is inaccurate, and it is better to replace it with the name "coloboma of the retina and choroid." To explain those cases where the presence of the retina at the site of the coloboma is anatomically proven, Hippel assumes that the unevenly strong development and unevenly early disappearance of the mesoderm play a role there. A coloboma of the optic nerve is the result of insufficient closure of the stalk of the optic vesicle; the depression that is usually present in the lower part of the disc with a coloboma also speaks for this. Of the various explanations for the development of coloboma of the lens, the views of Hess are most confirmed, according to which the growth of the lens can be hindered by the long persistence of individual vessels of the tunica vasculosa lentis.
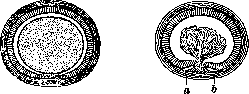
Figure 5.
Figure 6.
Figure 5. On the lower side of the optic vesicle, the fissure is widely open, and the mesoderm penetrates into the eye to the lens. Figure 6. The fissure of the optic vesicle is narrower, and the process of the mesoderm extends into the eye. The edges of the optic vesicle have curled so that the inner layer has bent outward and only at some distance from the fissure passes into the outer layer (at a and b). The fissure preserved in the latter is therefore larger than the fissure of the optic vesicle itself. In the developed eye, therefore, a large area will be devoid of pigment and will appear white.
A. Pokrovsky. Congenital colobomas of the iris and choroid, being a genotypic disease, are often observed in members of the same family (see the summary by Clausen). There are descriptions of families in which inheritance has been traced up to 5 generations (Snell, Loeb). In the latter case, the coloboma of the iris was atypical (directed upward). Since in the same family, a coloboma is observed either only of the iris or (more often) simultaneously of the choroid (a case, for example, of Hessin, who observed coloboma of the iris and choroid in three sisters, and coloboma of only the iris in two of their brothers), it should be assumed that both are caused by the same gene,
varying in its phenotypic manifestation. These fluctuations can also be very strong quantitatively, giving either aniridia (complete absence of the iris) or only a small defect of it. (Figure 7 confirms this position.) Phenotypic variation also explains the fact that in the same person, a coloboma is sometimes observed in one eye and aniridia in the other. An analysis of the pedigrees available in the literature speaks more for a dominant character of inheritance. Whether this applies to all cases, and whether all dominant cases are caused by the same gene—it is impossible to say at the present time. Colobomas are not subject to treatment, and one can only speak of the correction of refractive anomalies and the protection of the eyes from bright light with the help of colored glasses. Colobomas of the eyelids are corrected surgically.
Figure 7. Coloboma of the iris and aniridia, according to De Beck (from Clausen).
Unknown gender
Related articles
Mentioned in
Cite this page
“Coloboma.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/coloboma/