Childbirth
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928-1936 Soviet Medical Encyclopedia covers various aspects of childbirth, including obstetric shock, sudden maternal death, embolism, physiological effects on the female body, and premature artificial delivery.
Encyclopedia article (1928–1936)
257 XIX. Obstetric shock, sudden death of parturient women, puerperal women (embolism) . .
260 XXI. The effect of childbirth on the woman's body ....
271 XXIII. Artificial premature childbirth . .
272 1. Definition of the concept. Changes in the body during childbirth. Causes of the onset of labor. Childbirth is a physiological process as a result of which the entire egg detaches from the maternal organism, i.e., a mature fetus capable of extrauterine existence, together with all its appendages (secundina). As in every biological process, it is sometimes very difficult to draw a sharp, clear line between normal and pathological conditions, and therefore various authors, interpreting different variants of the mechanism of childbirth or generally any more or less significant deviations from their typical course, classify them—some as normal, others as pathological cases. Difficulty in predicting normal childbirth. If 'normal' is generally a very conditional and relative concept, then in its application to childbirth it turns out to be extremely elastic, depending on many reasons, and sometimes on completely accidental moments whose role cannot always be foreseen in advance. Even in the presence of certain obvious anatomical or functional anomalies which a priori should have affected both the normal course of the act of childbirth and its final outcome, childbirth can still fit within the framework of a purely physiological process and end successfully in all respects. On the other hand, even in the presence of anatomical-physiological prerequisites for a normal course, completely unexpected and unforeseen complications can occur during the act of childbirth, which can give a certain pathological deviation to one or another moment of this very complex physiological process. Childbirth is a general manifestation of life of the entire organism taken as a whole, and by no means a local process occurring only in the sexual sphere; they place heightened demands on all organ systems, on all active and hidden reserve forces of the female organism, and on all its life resources in general. Therefore, childbirth as a very multifaceted dynamic process requiring maximum, often extreme, tension of all the life forces of a woman, easily reveals any, often deeply hidden, defectiveness and inadequacy of her organism—both purely anatomical and functional (in particular biochemical). Static and dynamic-biological constitutional factors and their influence on the main components of childbirth. For the completely normal course and completion of the act of childbirth, of course, a normal state and action of all its main components (birth canal, birth object, and birth forces) are required, and above all, the correct harmonious ratio between them; however, the latter can be fully ensured only on the condition of a certain completeness of the entire organism as a whole. Therefore, various, even minor constitutionally pathological deviations, and all the more so already clearly expressed constitutional anomalies, can imprint a more or less sharp pathological mark on individual organ systems and their functions and thus affect all the main components of the act of childbirth, i.e., on the very structure of the birth canal, on the nature of the action of the birth forces, and directly or indirectly on the birth object, and consequently ultimately on the general outcome of childbirth (e.g., a narrowed pelvis in a woman with an infantile deviation or weak labor activity in a woman with an asthenic deviation can, due to spatial mismatch and because of the longer course of childbirth—and thus greater trauma to both mother and fetus—lead to various complications, some standing only on the border between normal and pathological, others already clearly pathological). Thus, the belonging of a woman to one or another constitutional type can to a certain degree influence the outcome of childbirth. III Significance of other, especially socio-domestic factors of motherhood. Determining significance are also racial, national, and age differences, and a whole series of other quite diverse individual peculiarities. However, dominant is the entire external environment in the broad sense of the word, surrounding the woman throughout her life path (starting from the first days of her life and ending with pregnancy and childbirth). The importance of all factors of a social order becomes obvious if one takes into account the conditions of growth and upbringing (especially the importance of rickets in the pathogenesis of pelvic anomalies), the general development of the organism, cultural-hygienic habits of the woman, physical culture, conditions of nutrition and housing, all professional and domestic moments, acquaintance with the sanitary minimum in the field of protection of motherhood and infancy, the woman's own attitude toward impending motherhood, greater or lesser rest before childbirth, provision of proper observation throughout the entire pregnancy, all preventive measures, and finally proper obstetric help at the right moment. Childbirth in woman from the point of view of comparative physiology and anthropology. Emptying the pregnant uterus of its contents, although representing a very complex physiological act, nevertheless has something in common with emptying the intestine and urinary bladder, at least to the extent that all these hollow organs are built from smooth muscle tissue (differing in their contractile activity by very characteristic features) and since their emptying takes a more or less active part of the abdominal press. This similarity is striking in lower mammals, where the expulsion of products of pregnancy occurs simply, easily, and quickly. In higher mammals this analogy gradually becomes less and less noticeable, as the mechanism of the act of childbirth gradually, as it approaches the human being, becomes more and more complicated. In connection with the changing ratio of parts of the fetus and with the modification of the shape of the pelvis as the birth canal and support for the entire trunk and lower extremities, obstacles gradually increase for the forward movement of the fetus and especially of its head end, which requires the participation in the act of childbirth of a number of auxiliary means and the involvement of the entire organism in the work of childbirth. In man, due to the relatively greatest predominance in the development of the brain, the head of the fetus is already so relatively voluminous that in its passage through the small pelvis it completely fills it, so closely touching everywhere against its walls that even a slight narrowing of it can significantly retard its forward movement as the most voluminous and densest part of the fetus. The birth canal as a whole (hard and soft birth passages). In order to understand the course of physiological childbirth and to penetrate into the very essence of their mechanism, one must first start from a clear concept of the individual components of this complex physiological act, of their essential properties and peculiarities, taken in the resting state, i.e., immediately before childbirth. The first component, pre-existing independently of pregnancy and childbirth—purely anatomical (predominantly static): this is the pelvic canal, the bony pelvic ring as a constant magnitude, almost not changing during the act of childbirth—the so-called hard birth passages. The supplement and as it were the direct continuation of the bony birth canal are the soft birth passages, which are formed only in the process of the act of childbirth, when under the pressure of expelling forces the forward-moving head stretches to the maximum limits all the musculature of the pelvic floor, its fasciae, the lower segment of the vagina, and the skin of the perineum, bulging all this together in the form of an 'additional outgoing cutaneous-muscular tube,' through which the entire fetus must pass as through the soft part of the birth canal. Normal spatial relations of the small pelvis. Taken in a skeletonized form the pelvis has the appearance of an almost solid bony ring (composed of the iliac, ischial, pubic bones and the sacrum together with the coccyx), closing a cavity, or canal, with a relatively voluminous entrance and a somewhat smaller exit. The spatial relations of this canal are not the same throughout its entire extent: since its side walls converge downward, it is somewhat narrowed in the transverse direction. A sagittal median section through the pelvis shows that its anterior wall, formed by the pubic bones, is much shorter than the posterior wall, formed by the sacral bone, and that due to the curvature of the anterior surface of the sacrum the entire pelvic canal is arched forward. The entrance to the pelvis has the shape of a transverse ellipse with a slight narrowing downward. It is bounded behind by the sacral promontory, on the sides by the linea terminalis, in front by the upper edge of the symphysis. The anteroposterior diameter of the entrance, i.e., the shortest distance from the sacral promontory to the nearest point on the posterior surface of the symphysis—the true or obstetrical conjugata (conjugata vera, s. obstetrica)—is 11 cm. The distance from the sacral promontory to the upper edge of the symphysis (1/2 cm more) is called the conjugata anatomica. (Measurement of pelvic dimensions—see Obstetrical examination). Its transverse diameter—the distance between the most distant points of the linea terminalis—is 13 cm. The right oblique diameter—from the right sacroiliac articulation to the left iliopectineal tubercle—is 12 cm. The left oblique—from the left sacroiliac articulation to the right iliopectineal tubercle—is also equal to 12 cm.
The pelvic outlet is bounded by the pubic arch, the ischial tuberosities, and the tip of the coccyx. Its anteroposterior dimension—from the lower border of the pubis to the tip of the coccyx—is 9.5 cm, but during childbirth, due to the backward displacement of the coccyx, it increases to 11.5 cm. The transverse dimension—the greatest distance between the ischial tuberosities—is 11 cm. By the pelvic cavity and specifically its middle part is meant that segment of the small pelvis which is located at the midpoint between the inlet and the outlet; it corresponds to the level below which the pelvic canal begins to change its direct direction downward and curves forward. Its anteroposterior dimension—from the point where the sacrum bends at the level of its third vertebra to the middle of the pubic symphysis, as well as its greatest transverse dimension—is 12 cm. Relative mobility of the pelvic joints. In addition to the above-mentioned increase in the anteroposterior dimension of the pelvic outlet (which is explained by the fact that the coccyx, due to the mobility of its joint with the sacrum, is pushed backward by the pressure of the fetal head), the most important obstetrical dimension of the pelvis, i.e., the anteroposterior dimension of the pelvic inlet—conjugata vera—also changes (though to a much lesser extent, approximately by 1/2 cm) in certain body positions, which Balandin demonstrated on cadavers, and Walcher by careful measurements on living subjects (see Walcher's hanging position). Finally, the concentric expansion of the entire pelvis as a whole, although very slight, has also been proven by the research of Loeschke. This is explained by the general loosening of tissues observed during pregnancy, affecting not only the soft tissues but the entire ligamentous apparatus and joints; it causes relatively greater mobility of both the sacroiliac and the pubic symphysis joints. All these data concerning the relative, although very slight, mobility of the pelvic joints should of course not be overestimated. Nevertheless, these data may play, although not visible to the eye, still a definite role. Geometric scales in application to the pelvis. The significance of the system of parallel planes according to Hodge. For the most vivid representation of the spatial relationships of the small pelvis (which is the only one that has significance from the mechanical point of view of childbirth), attempts have long been made to approach them with one or another purely geometric scale, using various mentally projected planes passing through different parts of the pelvis. Undoubtedly, all such planes are by no means such from a purely geometric point of view, and therefore such classics of obstetrics as, for example, Bumm, were skeptical of them, asserting that they by no means contribute to the theoretical understanding of the act of childbirth and cannot serve as a practical guide at the bedside of the parturient. Nevertheless, when speaking of the spatial relationships of the small pelvis, one cannot ignore the system of parallel planes proposed by Hodge, namely the following: the first parallel plane (terminal) corresponds to the plane of the pelvic inlet, the second corresponds to the level of the lower border of the symphysis, the third (spinal) corresponds to the level of the ischial spines, the fourth corresponds to the coccyx and the pelvic floor (Fig. 1). The use of these mentally projected planes (the distance between each two of them averages 3-4 cm) makes it easier to orient oneself at any given moment of childbirth in the spatial relationships between the pelvis and the presenting part of the fetus (usually the head) and to judge fairly accurately the height of its standing at one or another level of the pelvic (resp. birth) canal.
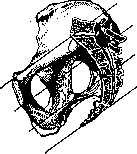
Figure 1. System of parallel planes according to Hodge.
A detailed study of Hodge's parallel pelvic planes has shown that the pelvic cavity by no means represents a curved canal directed anteriorly and superiorly, but rather corresponds to a cylinder obliquely cut inferiorly and anteriorly. Corresponding to such a shape of the pelvic cavity, the fetal head passes through the pelvis not in the direction of a line that is constantly curving anteriorly, as was thought earlier, but is pushed under the pressure of the forces of labor first straight downward, moving in the direction of the axis of the pelvic inlet and gradually passing one after another all the above-mentioned 4 parallel planes up to the pelvic floor (and only here does the birth canal change its direction, see below). Axis of the pelvic inlet and pelvic axis (pelvic guide line). By the axis of the pelvic inlet, one must understand a line mentally drawn through the center of the pelvic inlet in a perpendicular direction (if extended downward, it would reach the coccyx, and upward—approximately to the navel). This term, "axis of the pelvic inlet," should in no way be confused with another term, "pelvic axis," which is a synonym for the concept of "pelvic guide line." By these last two equivalent terms, one must understand a line mentally drawn through the midpoints of all the straight diameters of the lesser pelvis. This line practically serves for orientation regarding the given position of the presenting part (i.e., anteriorly or posteriorly, to the left or to the right of the guide line). From what has been stated, it is clear that the guide line only at its beginning almost coincides with the direction of the axis of the pelvic inlet, and specifically up to the middle of the pelvic cavity; here, however, it begins to curve anteriorly quite sharply and for a long time, corresponding to the curvature of the pelvic canal. -Pelvic inclination. Since the promontory in the vertical position of the woman stands significantly higher than the upper edge of the symphysis, the plane of the pelvic inlet has an oblique direction in relation to the horizon: it is inclined anteriorly and inferiorly. The angle formed by the plane of the pelvic inlet with the horizontal plane is called the pelvic inclination; in the standing position of the woman, it is equal to 60°. Soft birth canal, pelvic floor or pelvic diaphragm and urogenital diaphragm. The concept of the spatial relationships of the birth canal changes significantly if, instead of a skeletonized pelvis, one considers the pelvis as a whole, i.e., together with all its soft parts. At the same time, it is immediately striking that the upper segment of the pelvic cavity is spatially not at all limited by soft parts, whereas the pelvic outlet is closed by a group of tightly stretched and flatly arranged muscles—the pelvic floor, or pelvic diaphragm—through which only the exit openings of the intestine, genital, and urinary tracts pass. The main mass of this diaphragm is formed by the muscle bundles of the levator ani, which, starting from the tendinous line at the lateral and anterior walls of the pelvis, stretched along the plane and divided on each side into two parts (portio pubica levatoris ani and p. iliaca), go to the coccyx and to the fibrous bridge in front of it. Here the bundles coming from both sides join together, leaving, however, a free slit in the middle for the passage of the intestinal tube and the vagina. To the m. levat. ani on both sides posteriorly, bundles of the m. ischio-coccygei are also added, running fan-like from the spina ischii to the coccyx. On their upper and lower surfaces, all these muscle bundles are lined with dense fascia (fascia sup. and infer. of the pelvic diaphragm). Examination of the pelvic floor from below shows that in front of the described diaphragm there is another, as it were, additional, so-called urogenital diaphragm, consisting of transversely running bundles of the m. compressoris urethrae and m. transversi perinaei profundi, as well as the musculature closing the vagina (i.e., m. bulbo-cavernosus = m. constrictor cunni and m. ischio-cavernosus) and closing the anal opening (i.e., m. sphincter ani externus). Only during childbirth, under the pressure of the head, the muscles of the pelvic floor smooth out, stretch, and move apart, thus forming an additional muscular tube, constituting a continuation of the bony birth canal (equal in length to it, and in width corresponding to the dimensions of the fetus). The stretching of the pelvic floor and the formation of this muscular, or rather skin-muscular tube from the unyielding tissues of the perineum requires a very significant expenditure of labor forces, especially in primiparas. Birth object. By the birth object, one must understand the entire contents of the uterus at the end of pregnancy, and in doing so, first of all, proceed from a correct understanding of it as a whole, taken in a resting state, i.e., immediately before childbirth. Individual parts of the fetal egg are not equivalent in their physical properties, since they are either liquid (amniotic fluid), or more or less soft (fetal membranes, all secundina), or hard (skeleton). All these parts of the fetal egg are distinguished by far from identical "deformability." Only thanks to the fact that the entire fetal egg, taken as a whole, is distinguished by a, although not identical in its various parts, but in general still very significant deformability, is a uniform transmission of intra-abdominal pressure during childbirth possible through the uterine walls to the entire contents of the uterine cavity, and consequently the effect of the latter (placed under conditions of increased pressure) in the direction of least resistance, i.e., directly on the exit opening of the uterus as a fetal container—on its internal os. Of course, amniotic fluid, like any liquid medium, is distinguished by the above-mentioned physical properties to a much greater degree than all other more or less dense constituent parts of the fetal egg. The more amniotic fluid there is, the more easily the entire uterine content is deformed, and if one has in mind the body of the fetus itself, then those parts of it that contain the greatest amount of fluid are most easily deformed (a substantial difference between its soft and bony parts). Therefore, during childbirth, the lower pole of the fetal sac usually turns out to be presenting (leading), as the part most easily yielding to pressure and therefore deforming first of all. Fetal head. The main part of the birth object is the entire body of the fetus, but the most essential significance, of course, belongs to the head as the most voluminous, dense, and unyielding part, and therefore relatively slowly deforming. On the fetal head, as on the head of an adult, one must distinguish the cranium (the significantly predominant part in size) and the face. The cranium consists of paired frontal and parietal bones, the occipital bone, the squamous parts of the temporal bones, and the wings of the sphenoid bone, which together constitute a bony capsule of ovoid shape. Between these bones exist thin fibrous connections, so-called sutures, and specifically the following: 1) sagittal (sutura sagittalis) between the parietal bones, 2) frontal (sut. frontalis) between the frontal bones, 3) coronal (sut. coronalis) on each side between the frontal and parietal bones, 4) lambdoid (s. lambdoidea) between the parietal and occipital bones. (Temporal and sphenoid, or mastoid sutures have no practical significance.) -Fontanelles. Where two or more of these sutures meet each other, more or less significant gaps remain, covered by fibrous membranes and called fontanelles: 1) large, or frontal (fonticulus frontalis), with rhomboid outlines, at the place where the sagittal, frontal, and both branches of the coronal suture meet; 2) small, or occipital (fonticulus occipitalis), at the place where the sagittal and lambdoid sutures meet; this is not properly a free gap between the bones (at least in a mature fetus), but rather a small, triangular-shaped depression between the parietal and occipital bones, clearly palpable only during childbirth; 3) on the anterior and posterior parts of the squamous part of the temporal bone on each side lie two more lateral fontanelles, which, however, are practically of little importance. All these sutures and fontanelles significantly facilitate spatial orientation regarding the position of the head in one or another part of the pelvis and therefore serve as important landmarks during childbirth. Dimensions and circumference of the head. For understanding the very essence of the mechanism of childbirth, it is essentially necessary to also know the following dimensions and circumferences of the head as average values in a full-term mature fetus: 1) straight dimension, or diameter (diameter fronto-occipitalis)—from the glabella to the most distant point of the occiput—12 cm, 2) large transverse (d. biparietalis)—distance between both parietal eminences—9 1/2 cm, 3) small transverse (d. bitemporalis)—greatest distance between both branches of the coronal suture—8 cm, 4) large oblique (d. mento-occipitalis)—from the chin to the most distant point of the occiput—13 1/2 cm, 5) small oblique (d. suboccipito-bregmaticus)—from the suboccipital fossa to the large fontanelle—9 1/2 cm.
Furthermore, the following circumferences are distinguished: 1) the straight (circumferentia fronto-occipitalis), corresponding to the straight diameter and equal to 34 cm; 2) the large oblique (c. mento-occipitalis)—corresponding to the large oblique diameter, equal to 35 cm; and 3) the small oblique (c. suboccipito-bregmatica)—corresponding to the small oblique diameter, equal to 32 cm, consequently the smallest and therefore the most important from the point of view of the mechanics of childbirth. Taken as a whole, the head represents, as it were, a biaxial or rotational ellipsoid (Sellheim) with an insignificant predominance of the long axis over the short one, whereby the long axis of this head ellipsoid forms an angle with the cervical vertebrae, the magnitude of which changes depending on the peculiarities of the engagement of the head into the pelvis during childbirth (A. Muller). Since, under the influence of labor forces, the head is compressed to a certain degree and therefore generally changes its shape, then by virtue of this (individually variable) plasticity of it, all the above-mentioned numerical data—diameters and circumferences (precisely established, of course, only on the head of an already born fetus)—can vary significantly during childbirth in each individual case and therefore have the significance only of approximate average values. With significant variability of the entire 'shape of the head,' its total volume, on the contrary, remains relatively little changeable; only with very strong compression is a certain outflow of fluid from the cerebral ventricles into the spinal canal and a corresponding insignificant decrease in total volume possible (Fehling). Of much greater importance than the absolute values of all the named diameters and circumferences of the head is its spatial relation to the pelvis, and the most important, often decisive role is played by both its position and its property of being modeled, of adapting to the dimensions and shape of the given pelvis, thanks to which, even in the presence of significant spatial disproportion, its engagement into the pelvis is possible with the most suitable, i.e., precisely the smallest, diameter (resp. circumference). Configurational properties of the head. The significant deformability of the head during childbirth or (using the generally accepted term here) its configurational ability is explained by the peculiar construction of the fetal skull from several relatively thin bone plates, which, under the pressure of labor forces, can to a certain degree bend, overlap one another, and thus move relative to one another quite significantly. This is possible only thanks to the above-mentioned sutures as fibrous, relatively easily yielding, mobile connections between the individual bones of the skull. When the head, during its forward movement, encounters significant obstacles from hard or soft, often still little yielding, rigid parts, it can, after a more or less prolonged adaptation, configure well, i.e., assume the shape necessary for the given moment and place, more corresponding to the size and shape of one or another part of the birth canal; as a result of this, even a relatively large spatial disproportion and, generally speaking, an obstacle can be smoothed out and overcome. However, configuration of the head is possible only within known limits—only under the condition of regular, very energetic, and often quite prolonged labor activity. Fetal torso. Compared with the head, the fetal torso as a part of the birth object has much less significance. The largest transverse diameter of the shoulders is 12 cm (their corresponding circumference is 35 cm). The largest transverse diameter of the hips is 9 cm (the corresponding circumference is 27 cm). Since these relatively soft parts of the torso are easily compressed and displaced at the moment of passage through the pelvis, then, with rare exceptions, they usually do not constitute a mechanical obstacle during childbirth. A full-term mature fetus, fully extended in length, should be about 48–52 cm and weigh on average about 2,800–3,200 g. It is necessary, however, always to remember that, on the one hand, there are surprisingly light but undoubtedly full-term, and on the other, relatively heavy but clearly premature fetuses; from this it is clear that the concepts 'mature' and 'full-term fetus' are not always identical. Flexibility of the fetal spine and its significance in the mechanism of childbirth. From the point of view of the mechanics of childbirth, the greater or lesser flexibility of the entire fetus as a birth object, caused mainly by the flexibility of its spine, is of significant interest. Only in 1904 did Sellheim, in a whole series of experiments (carried out with all precautions and controlled radiographically) on living newborns using a quadrant and a dynamometer, comprehensively study this question and arrive at the following important conclusions. The flexibility of the child's spine is relatively very great (thanks to the greater content of cartilaginous tissue in it, greater elasticity of the ligamentous apparatus, etc.). The greatest flexibility is observed in the cervical part of the spine, which is explained here by the lower, less developed vertebrae and the very easy mobility of the joint articulation with the head. In individual segments of the newborn's spine, flexibility in different directions turned out to be indeed unequal; the greatest flexibility (its facillimum) of the cervical part is backward, of the thoracic region is to the sides, of the lumbar is to the sides and backward, of the sacrolumbar is forward and backward.—Joints. For the course of childbirth, the very significant mobility of the joints of the shoulder and pelvic girdle is very important. Mobility in the shoulder, acromioclavicular, and sternoclavicular joints is so great that the humerus bones can freely be brought into contact on the chest, whereby the shoulder blades move strongly upward (an attempt to push the fetus's arms toward the back always encounters strong resistance). The fetus's thighs can easily be thrown back onto the abdomen and folded parallel to each other (as in breech presentation). Expulsive forces. The main source of labor forces is the uterus; as a motor smooth-muscle hollow contractile organ, extremely hypertrophied at the end of pregnancy and therefore fully suitable for very energetic mechanical work, it plays, in the full sense of the word, the role of a birth motor. Strictly speaking, this function is performed not by the entire uterus as a whole, but only by its upper section, i.e., its body (the actual fetal receptacle), the walls of which represent a thick, dense network of strong muscle fibers closely intertwined in various directions, forming with their entire mass the so-called hollow muscle; it is precisely this section that is the main and very powerful expulsive organ. The isthmus (isthmus; according to Aschoff), i.e., the section located between the body and the cervix of the uterus, already involved from the middle of pregnancy in the composition of the fetal receptacle, and the cervix of the uterus, which remains in an unchanged state until the beginning of childbirth, do not have a direct relation to the birth motor. These sections, with weak, sparse muscle fibers, play a secondary, significantly smaller role compared to the hollow muscle. Capable not so much of active contractions as of passive maximal stretching, they only indirectly assist the forward movement of the fetus, being part of the 'exit tube.' From a purely mechanical point of view, it is quite understandable that if all sections of the uterus contracted during childbirth equally strongly, then the forward movement of the fetus toward the direction of least resistance and its expulsion itself would be impossible.—As auxiliary labor forces, the following function: 1) the ligamentous (suspensory) apparatus of the uterus, especially the round uterine ligaments, which are strongly hypertrophied by the end of pregnancy and rich in smooth muscle fibers, and 2) powerful contractions of the striated musculature of the abdominal press. Of secondary importance, especially during difficult childbirth, are contractions of the muscles of the entire torso (torso press). And finally, when at the end of expulsion a significant part of the fetus has already passed through the vagina, then the crowning of the rest of it, as well as the exit of the afterbirth, are indirectly helped by contractions of the smooth muscle fibers embedded in the hypertrophied walls of the vagina. Experimental data on the physiology of the uterus. Experiments on the uterus, both in vivo and on an isolated organ, conducted by a whole series of authors (over the last three decades with a methodology significantly improved compared to earlier times, guaranteeing the accuracy and objectivity of the results obtained), have made it possible to study in detail the physiology of uterine contractions in general and, in particular, have provided much of interest from the point of view of the physiology of the act of childbirth. It has been proven that the uterus, even outside the state of pregnancy, but especially during and toward the end of it, possesses the ability for more or less regular and strong automatic contractions. This property is inherent to it, as to any other smooth-muscle organ, but to a much stronger degree. The initial impulses for these automatic contractions arise (as can be seen directly on an isolated organ) usually in the very upper sections of the genital tract. From there, they propagate peristaltically in a wave-like manner in the direction toward its exit.
Contractile waves are not limited to the uterus alone; usually, they more or less simultaneously involve the entire contractile system of the genital apparatus in general, i.e., not only the entire genital canal but also the fixing (suspensory) ligamentous apparatus. Automatic contractile work of the round uterine ligaments and its significance during childbirth (in experiment). In experiments on an isolated rabbit uterus (and especially on a pregnant one), Kurdinovsky often had occasion to observe that the round uterine ligaments, actively participating in the contractions of the uterine horns, strongly pull and hold them, sometimes for 1/2 a minute, "in suspension" ("as if on reins"); by fixing them in this way in the anterior direction, they enable the uterus to better utilize its contractile work. This active role of the round ligaments is especially striking when observing the act of birth in an isolated rabbit uterus; during the entire time of the progressive movement of the fetuses along the genital canal, energetic contractions of the round ligaments are observed, contributing to the act of birth; contracting strongly, they lift the uterine horns, giving them a firm point of support (in vivo this point of support is even firmer, as the uterus is thus fixed directly in the direction of the anterior wall of the pelvis, i.e., to the place of attachment of these ligaments). Automatic contractions of the broad uterine ligaments and their significance during childbirth (in experiment). By fixing the entire uterus and bringing it closer to the exit of the genital canal, the round ligaments facilitate the uterus's expulsion of its contents. The broad uterine ligaments also take an active part in the contractile work of the uterus. Only upon superficial observation does it seem that they move purely passively due to the fact that the contracting uterine horns draw them into motion. Upon more careful observation, however, one can undoubtedly be convinced that, in addition to these passive movements, they also possess the ability for completely independent active contractions, which occur automatically, independently of the contractions of the uterine horns; in such cases, somewhere in one place of the broad ligament or in several simultaneously, an initial impulse for movement arises in the form of a peculiar play of fibers, which then quickly engulfs the entire ligament. The broad ligaments exhibit even more significant activity in the pregnant uterus, especially during the act of birth observed in an isolated organ. By direct observation here, it is easy to be convinced that they contribute to the expulsion of the fetus with their contractions. This happens as follows: when the fetus is forced into the underlying section (into the upper part of the vagina) by the contractions of the uterine horns, the broad ligament, which was previously at rest, begins to contract in a direction transverse to the axis of the genital canal; by these contractions, it is imparted a progressive movement in the direction of least resistance, i.e., toward the exit of the genital canal; thus, the broad ligament, with its ring-shaped contractions, as it were, squeezes out the fetus; under the pressure of this vis a tergo, it moves further. It is, of course, difficult to say to what extent experimental data on the question of automatic contractions of the uterus and its ligamentous apparatus can be transferred to the human uterus. Regarding the nature of the contractions of the woman's uterus in general and in particular during childbirth, the opinions of individual authors still differ greatly. The anatomical complexity of its muscular structure (compared to the uterus of animals) already a priori gives reason to think about the greater versatility of its contractile work and therefore forces us to be cautious in drawing corresponding analogies. Nevertheless, clinical observation with the naked eye (the most reliable because any artificial irritation is excluded here) shows that in women, too, impulses for labor contractions usually arise in the upper section of the genital canal, i.e., in the fundus of the uterus; it is here that, especially at the beginning of childbirth, the primary hardening of the uterine musculature occurs as a sign of beginning contraction. In the further course of childbirth, contractions also arise in the region of the cervix. Many authors believe that usually the initial contractile movement still arises in the fundus of the uterus and only from there does it propagate peristaltically toward the exit of the genital canal. According to others, it can primarily begin both at the place of attachment of the round uterine ligaments to the anterior abdominal wall (K. Schroder) and in the region of the broad uterine ligaments (Werth). The peristaltic nature of the contractions when palpating the uterus (at the beginning of a contraction) and during direct observation during a cesarean section is masked by the speed of the propagation of the contractile wave, as well as by the round shape of the uterus. However, Schatz, by inserting a manometer into the uterine cavity, nevertheless proved the peristaltic nature of its contractions. Experimental study of uterine contractions under the influence of various artificial irritations (of a physical and chemical nature). The experimental use of various artificial stimulants of the uterus as a contractile organ, i.e., mechanical, thermal, electrical irritations of it, as well as pharmacological agents and organotherapeutic preparations—both in experiments on an isolated organ and in vivo—made it possible to study in all details the physiology and pathology of uterine contractions. Pharmacological experiments on an isolated uterus were especially fruitful in this regard, since on an organ disconnected from all connections with the central nervous system, it was easier (especially when comparing them with in vivo experiments) to clarify the very essence of the action of various uterine agents, i.e., to study all the paths and methods of their influence. Thus, the experiment gave us the opportunity not only to study the uterus as a birth motor in detail but also taught us how to stimulate the work of this motor in various ways where necessary. Experimental verification of uterine contractions of reflex and psychic origin. Experiments on the uterus in vivo have shown that the uterus in its contractile activity is highly sensitive to various, even very distant reflex influences, i.e., to irritations both originating from some internal organs and applied somewhere on the periphery, for example, to painful irritations of any area of the skin in connection with subcutaneous or intravenous injections (and, moreover, completely independently of the composition of the injected liquid). Therefore, the well-known fact of uterine contractions under the influence of mechanical irritation of the nipples is by no means some specific phenomenon sui generis, but is only one of the numerous examples of such reflex contractions. It is easy to be convinced of this purely reflex nature, since in an experiment, under conditions of deep anesthesia, when all reflexes in general are suppressed, such contractions no longer occur, even with very strong irritations. Experiments in vivo also empirically confirmed the long-known possibility of uterine contractions under the influence of purely psychic excitations, e.g., as a result of fright (Kurdinovsky). As for uterine contractions under the influence of artificial irritation of various parts of the central nervous system, there are very extensive but rather contradictory experiments on this issue, which already has a direct bearing on the complex and still far from resolved problem of uterine innervation (see Uterus-innervation). By applying mechanical or electrical stimulation to any part of the cerebral cortex and various other parts of the cerebrum, medulla oblongata, and spinal cord throughout its entire length, various authors obtained more or less strong contractions of the uterus (and sometimes, conversely, its relaxation). It must be thought that the central nervous system exerts its regulating influence on the uterus, sending impulses of both a stimulating and inhibitory nature to it. So far, we do not have sufficient grounds to assume the existence of any topographically precisely localized single main center in charge of the contractile work of the uterus; rather, one can assume the presence of several such motor centers in the central nervous system. However, the uterus in its contractile activity is, generally speaking, highly autonomous and independent of the cerebrospinal nervous system. It is very likely that its contractions, both those that occur automatically and those that are induced artificially, depend to a significant extent on the local nervous apparatus of the uterus. Significance of local (uterine and para-uterine) nervous apparatus. Recently, the presence of bipolar and multipolar ganglion cells in the uterine walls has been proven. In the muscular layers of the uterine fundus, there are in any case many ganglia lying subserosally; this obviously explains why the uterine fundus is extremely sensitive to any external irritations during childbirth and especially after the expulsion of the fetus and always reacts to them with strong contractions. Of course, those nervous apparatuses that lie in the vicinity of the uterus also play an important role, and first of all the so-called.
The Frankenhauser cervical nerve plexus, rich in ganglia, connected with sympathetic and parasympathetic (and probably spinal) nerves, sends out branches that supply the entire uterus, but mainly its cervix. Paracervical and vaginal ganglia may also have a certain significance. Nevertheless, despite the presence of the aforementioned intrinsic nervous system (uterine and perimetrial), it is still difficult to say with certainty whether the automatic contractions of the uterus are neurogenic or purely myogenic in origin. A whole series of facts and data from the field of general physiology of smooth muscles provides many grounds for recognizing in smooth muscle tissue as such an independent, purely myogenic excitability and therefore a relative independence from any nervous influences, both central and local (peripheral). The significance of the latest experiments on the uterus with endocrine preparations for understanding its functions as a birth motor. In the current state of the complex and far from fully resolved problem of uterine innervation, one must, of course, take into account not only the purely "nervous" but also the "chemical," or rather "neuro-chemical," correlation. A priori, it is undoubted that the constant, essentially important exciters of the contractile work of the uterus must be various hormones, produced both by the sex glands and by other endocrine organs, which specifically influence the tone of its musculature in one way or another. Constantly circulating in the blood, they act either through the mediation of various nerve pathways on the entire neuromuscular apparatus of the uterus as a whole, or directly on its muscle fibers, or on its vessels, both through the vasomotor center and, bypassing it, directly on the vascular walls. The role of the uterine suspension apparatus. Although the round uterine ligaments apparently have only an indirect relation to the expulsive forces, having significance only as an auxiliary factor, nevertheless, their anatomical integrity and functional competence are a necessary condition for the proper and productive action of the birth motor itself. Actively participating in the contractile work of the uterus, they, by their contractions and the resulting shortening and tension, firmly fix it to the anterior abdominal wall, to the pelvis, and to the pelvic floor, and thereby limit the possibility of its movement in an upward direction. This fixing action of the round ligaments is especially striking when the uterus overcomes great resistance, i.e., in any spatial disproportion between the pelvis and the presenting part of the fetus. Meanwhile, it is already clear a priori that the round ligaments, the muscle fibers of which constitute a direct anatomical continuation of the uterine musculature (which has been proven by the histological studies of N. Ivanov) and therefore are part of the general contractile system of the genital apparatus, must eo ipso take part in the act of childbirth. This is all the more possible because by the end of pregnancy they, becoming strongly hypertrophied, turn into thick muscle cords, quite reliable and suitable for fixing the uterus during its expulsive contractile work. If this important role of the round ligaments has been established both by experiments on the uterus of animals and by clinical observations during childbirth (especially difficult and prolonged ones, when the tensed thick cords of these ligaments are easily palpable), then the same cannot by any means be said regarding the broad uterine ligaments. Although in experiments on an isolated uterus their active participation in contractile work, and especially during childbirth, has been established ad oculos, nevertheless, it is very difficult to say with certainty that they play the same active role in childbirth in women as in animals. Regarding the sacrouterine ligaments, there are neither precise experimental nor clinical data concerning their participation in the contractile work of the uterus; however, since they also contain smooth muscle fibers that hypertrophy during pregnancy, it must be thought that they also play a certain role in the sense of fixing the uterus in general and in particular during childbirth. One way or another, the fixation of the uterus by the entire ligamentous (suspensory) apparatus to the pelvic walls undoubtedly conditions the possibility of transmitting the action of all expulsive forces to the pelvis itself with all its contents. With the retraction of the uterus progressing during childbirth, i.e., with the gradual displacement of the hollow muscle upward and backward over the fetal egg moving in a forward direction, the suspension apparatus holds the uterus downward, pulls it toward the pelvis, and consequently acts in a direction opposite to retraction. It is precisely thanks to this that the uterus, being to a significant degree fixed, can work quite productively as an expulsive organ. If this fixation did not exist, then the forward movement of the fetus would be possible only to an insignificant degree, because the hollow muscle, during its contractions, would move more and more upward, i.e., would empty itself of its contents and therefore could not act upon it during the entire time of its contractile work. Only thanks to the tension that is produced by the entire suspension apparatus (and also, of course, after the effacement of the cervix) and the vagina, the upward movement of the hollow muscle is limited to a significant degree. As a consequence of this, the inevitable effect of an increase in intrauterine pressure during contractions must be the forward movement of the fetus only in the direction of least resistance, i.e., downward. The significance of the "seal." In the mechanism of the expulsive apparatus taken as a whole (i.e., the birth motor with all its auxiliary means, among which the abdominal press plays the main role), the so-called "seal" (Abdichtung; Sellheim) has a very important significance. The fact is that the actual transmission of abdominal pressure to the uterine walls, and through them to the fetus itself, is possible only when the uterus is pressed closely against the inner periphery of the pelvis in such a way that the outlet tube (at least its lower segment) is located in the pelvic cavity, and the entire remaining part of the uterus is in the abdominal cavity (this was proven with particular persuasiveness by Sellheim). Such a separation of the entire birth canal into two disconnected sections is obtained after full dilation of the uterus only because the outlet tube, stretching and encompassing the underlying parts of the fetus, fills the pelvic inlet to such an extent that at this place it lies closely against the inner periphery of the pelvis, coming into direct contact with it. The significance of this seal lies in the fact that during expulsion, the pressure of the abdominal press can be transmitted only to that part of the uterus which lies in the abdominal cavity; the part of the birth canal lying below the indicated seal is by no means subjected to the action of this pressure. Thanks to the fixation of the uterus to the pelvis, this pressure can be transmitted only in a downward direction, causing the expulsion of the uterine contents. Thus, the entire ligamentous apparatus fixing the uterus and the indicated hermetic seal mutually support each other. The significance of the abdominal press. The abdominal press functions as the main auxiliary apparatus of the birth motor, beginning to act with the start of the second stage of childbirth (the period of expulsion). Since, during strong bearing-down efforts, the respiratory muscles of the neck, chest, shoulder girdle, etc., simultaneously come into action along with the abdominal muscles as an additional auxiliary force, then, according to Sellheim, there is full justification to speak of a truncal press. Understanding the role of the abdominal press is facilitated if one imagines it as a voluminous, hollow, very powerful contractile organ surrounding the uterus, consisting of striated muscles. Of course, the abdominal press, while contracting, does not act directly on the uterus, i.e., immediately; it acts primarily on all the contents of the abdominal cavity as a whole, which, by virtue of this, finds itself in conditions of increased pressure (pressure of the abdominal press). If the intra-abdominal pressure were the same as the intrauterine pressure, these two pressures would counterbalance each other. In order for intra-abdominal pressure to exert an influence on the uterine contents, it must in any case be higher than the intrauterine pressure. This is supported by the studies of Sellheim, who convincingly showed that the contracting uterine walls can transmit the pressure they experience from all sides further, i.e., to their contents, only when the pressure acting on them from the outside exceeds the intrauterine pressure. According to manometric studies, intra-abdominal pressure is approximately twice as high as intrauterine pressure. The joint action of all expulsive forces as a whole. The division of the entire uterus into an upper active and a lower passive section (i.e., into a hollow muscle and an outlet tube), which takes place already during pregnancy, makes itself felt from the very beginning of childbirth; only thanks to this division does the functional transformation of the uterus from a resting fetal receptacle into an actively acting expulsive organ (birth motor) occur.
The productivity of the contracting uterus manifests itself in two directions: 1) since all its contents are placed under conditions of increased pressure, the lower pole of the fetal egg is naturally pushed toward the direction of least resistance, i.e., in the direction of the opening, toward the internal uterine os; 2) due to the shortening of the hollow muscle occurring during contractions, the muscle fibers of which run predominantly in a longitudinal direction, a pulling effect (in the sense of stretching) is exerted on the lower passive section; since its muscle fibers are located mainly circularly, as a result of this, they diverge to the sides, i.e., the cervix dilates. Thus, both these forces, acting in opposite directions (pressure from top to bottom, and pulling from bottom to top), in the general final result turn out to be equivalent, equally leading to the dilation of the uterus. By virtue of the simultaneous fixation of the upper active section of the uterus by all parts of the fixation apparatus, which hold it "as if on anchors," the expulsion of the fetus occurs relatively easily through the increasingly dilating cervical canal. Thanks to the aforementioned hermetic seal formed during the period of uterine dilation, by means of which the entire outlet tube is disconnected from the abdominal cavity and therefore is under conditions of lower pressure, the abdominal press, which begins to act in the period of expulsion, contributes to further maximum stretching of the outlet tube and at the same time energetically assists in the expulsion of the uterine contents—precisely because the intra-abdominal pressure increasing during labor pains, always significantly exceeding the actual intrauterine pressure, thereby serves as a powerful aid to the uterus as an expelling organ. Uterine retraction. An extremely important phenomenon inherent in the uterus, as in any smooth-muscle hollow organ, is so-called retraction. It is easiest to understand its essence by analogy with the urinary bladder, where this retractile rearrangement of fibers after its emptying occurs much faster and more sharply than in the uterus. The walls of the urinary bladder, which become very thin during its significant overfilling, thicken more and more as it empties and finally, upon complete emptying, collapse completely, almost reaching the thickness of a finger. Such thickening of them is the result not so much of the contraction of muscle fibers as of their mutual displacement and interlacing with each other. Exactly the same process occurs in the uterus. By virtue of their ability to retract, the uterine walls acquire, during the process of childbirth and immediately after it, very important plastic properties in a functional respect; only because of this can they adapt to all temporary states of uterine filling and, ultimately, to a significant reduction in its entire volume (long before those relatively very slowly occurring processes of involution begin, which subsequently lead to its final anatomically stable reduction in the postpartum period). This retraction of the uterus occurs without any special additional actual contractile work of its own (in the form of persistent contractions). From this it is clear that retraction and contraction are completely different concepts. It has been clarified that the effacement of the portio vaginalis, observed in the last months of pregnancy, is only an apparent phenomenon, caused by the fact that the fetal head (in a primipara in the 10th lunar month of pregnancy, usually entering the lesser pelvis) bulges the lower section of the uterine cavity and pushes the anterior vaginal fornix downward and to the sides to such an extent that it flattens significantly and is no longer felt as such. It is sufficient to push the head upward, and this fornix is immediately restored, and the portio vaginalis assumes its typical shape. This proves that the greater part of the cervix, and in any case its entire vaginal part, remains uneffaced until the beginning of childbirth. The dispute that lasted for many years about the so-called lower uterine segment can be considered resolved by Aschoff's research in favor of Bandl's doctrine. Aschoff proposed the following division of the uterus into 3 sections: 1) the body, 2) the isthmus, i.e., the upper third of the cervix, which, starting from the middle of pregnancy, becomes part of the fetal container, and 3) the cervix proper, which in no way enters into the composition of the fetal container from the beginning of childbirth. Thus, it is best to use the term "lower uterine segment" to designate that section of the uterus which stretches during childbirth under the influence of its contractions, and the term "contraction ring" to designate the boundary beyond which the hollow muscle begins. The influence of childbirth on the entire female organism. Childbirth brings the woman's organism out of a state of relative rest and more or less stable equilibrium, causes very significant, rapidly occurring changes in her reproductive organs, and requires a sudden and very significant exertion of all the woman's vital forces; it is natural, therefore, that such a complex physiological act must place significantly increased demands on the entire female organism, as a result of which more or less significant shifts occur in all organ systems, which, however, under normal conditions, have the character of transient changes and fluctuations that fit within the framework of a purely physiological amplitude. Only in the presence of one or another defect (purely anatomical) or inferiority of a functional nature can fluctuations occur that significantly exceed physiological boundaries and acquire pathological significance. However, here, as everywhere, it is often difficult to draw a clear line between physiology and pathology. The very significant tension of smooth and striated muscles associated with childbirth, sharp pain sensations, rapidly occurring changes in the volume of the uterus and the entire abdominal cavity, and inevitable blood loss—all this taken together places increased, extremely rapidly changing, and generally progressively growing demands primarily on the entire cardiovascular apparatus. During labor pains, the pulse rate noticeably increases; in the pauses, it returns to normal; however, at the end of the expulsion period, especially in a woman with an insufficiently stable neuropsychic sphere, it is difficult to establish a so-called constant pulse rate. The increase in pulse rate during labor pains partly depends on psychic excitement, partly on the increased work of the heart, which also manifests itself in a general increase in blood pressure; during labor pains, it reaches 40-50 cm H2O; much more significant fluctuations are also observed; they are greater the stronger and more painful the contractions are; the greatest rises occur during strong final pushing efforts, when they are noticeable even during anesthesia. After the rupture of the fetal bladder, the pressure drops 20-30 cm H2O below normal, and the more sharply, the more significant and rapid the discharge of waters was. During the crowning of the head, blood pressure rises sharply and then falls. Sometimes during childbirth, attacks of tachycardia, a feeling of lack of air, cardiac distress, etc., are observed even in persons with completely healthy circulatory organs. In general, it must be said that a healthy heart possesses sufficient reserve forces, which enable it to cope with the increased load. Breathing during childbirth is generally irregular. Already in the first stage, the frequency of respiratory excursions decreases during contractions and increases in the pauses (according to v. Winckel, the difference between these two phases is 6-8 breaths per minute). In the second stage, the fluctuations are even more significant. During pushing efforts (closure of the glottis)—inspiratory breath-holding; in the intervals between pushing efforts—accelerated, deep breathing. The further it goes, the greater the respiratory frequency in the pauses, and the less during pushing efforts (at the same time, the holding of it can be very prolonged, as a result of which severe cyanosis occurs). Changes in the blood during childbirth are so characteristic that, for example, Payer and others speak of a "labor blood formula." The increased work of the musculature directly related to childbirth, the indirect participation of many skeletal muscles, the loss of fluid associated with significant perspiration, and the resulting concentration of the blood—all this leads to an increase in all its components, which is expressed more sharply the stronger the contractions and pushing efforts are, and especially in primiparae. (In the postpartum period, in connection with blood loss, the blood picture changes, becomes unstable, obscured.) During childbirth, hypererythrocytosis is observed (by 1/2-1 million) with an increase in hemoglobin content, specific gravity, and alkalinity (Blumenreich), an acceleration of blood coagulation, continuously increasing and reaching its highest point in the placental stage (Neu, Schneider). Hyperleukocytosis (up to 4,500) is also typical, with neutrophilic polynucleosis predominating, which reaches its highest degree by the end of the second and especially the third stage (Pankow).
Payer explains this by the entry of foreign substances into the blood of the woman in labor.
Regarding phenomena from the gastrointestinal tract, first of all, the frequent occurrence of vomiting during strong contractions is well known, explained by reflex influences (displacement and tension of the peritoneum, pressure of the uterus on the solar plexus); sometimes vomiting with an admixture of blood (congestive hyperemia and reduced resistance of vessels, varicose dilation of veins in the gastric mucosa).
The stimulating reflex effect of uterine contractions on the peristalsis of the small intestine, the mechanical effect of the advancing head on the rectum, and the swelling of hemorrhoidal veins are also known.
How childbirth affects the functions of a normal liver has not yet been precisely clarified.
Due to spatial relationships, childbirth strongly affects the urinary organs.
There is a significant lifting of the urinary bladder upward and its displacement to the side, more often to the right (Martin).
Due to the compression of tissues, strong venous swelling, edema, and hemorrhages occur in it in the mucous membrane (especially in its neck).
The same can sometimes happen in the urethra, which is strongly compressed during pushing; by the end of the expulsion stage, urination becomes impossible.
However, during childbirth, urine secretion generally decreases, the specific gravity of urine falls, as well as the content of urea, sulfur, and phosphorus (only the amount of NaCl increases).
A not infrequent phenomenon is slight albuminuria, and sometimes the appearance of casts, erythrocytes, epithelium of the urinary tract, and acetone.
Information about the work of endocrine glands during childbirth is comparatively scarce.
It is known that the physiological hypertrophy of the thyroid gland, characteristic of pregnancy, increases even more (influence of venous hyperemia).
To what extent the changes characteristic of pregnancy in other endocrine glands (especially in the pituitary gland) also increase is not yet known.
Since childbirth represents the strongest and extremely intense (in a purely dynamic sense) general life manifestation of the organism, in which all its organs participate in one way or another, it is understandable that the general metabolism during the act of childbirth must undergo more or less significant changes; however, these important biochemical shifts and fluctuations have not yet been studied nearly enough.
Uterine activity during labor is associated with some heat production.
Schroeder, measuring the temperature of the uterus during childbirth, found that it is slightly higher than during pregnancy (by 0.1°).
During contractions, the temperature is higher than in the pauses; the difference is 0.02-0.10° (Frankenhauser, Henning).
However, childbirth as a general life manifestation also reflects on the general body temperature; it rises strongly in connection with the intense work of the abdominal press and many other auxiliary functioning skeletal muscles, but since significant heat dissipation also occurs during childbirth (due to the rush of blood to the skin, increased perspiration, sweating, accelerated deep breathing), thanks to all these regulators, excessive heat production does not ultimately occur.
Nevertheless, all the indicated thermoregulation sometimes turns out to be insufficient, and then the temperature rises noticeably.
In prolonged difficult childbirth, this increase can reach 38° and even higher.
In some cases, on the contrary, a drop in temperature is observed even before childbirth, but usually this happens only after the expulsion of the fetus; sometimes at this time, due to strong heat loss (thanks to exposure and cooling of the body, increased preceding secretion of sweat and its evaporation), chills are observed, sometimes shaking, although short-lived, having no pathological significance (see below - fever during childbirth).
Causes of the onset of childbirth. Mauriceau explained the onset of childbirth by a sharp increase in uterine tone, which is a natural reaction to its prolonged stretching during pregnancy.
This assumption, finding some confirmation in the fact of premature childbirth in twins and hydramnion, does not withstand criticism, however, because in normal conditions there can be no talk of either passive stretching of the uterine walls or the subsequently occurring tension of them, since the uterus hypertrophies during pregnancy and its enlargement is an actively occurring process of growth, and not a passive, purely mechanical stretching of its walls.
According to other, also old authors (Petit, Dubois, Kilian, etc.), childbirth occurs due to the pressure of the presenting part of the fetus on the lower segment of the uterus.
However, the possibility of such isolated pressure with an intact fetal bladder must be rejected, since the intra-ovular pressure is equally uniform everywhere and cannot be one-sided; therefore, even in transverse position and with a high-standing head, where such pressure is absent, childbirth is usually on time, and not delayed.
In 1812, Naegeli first, and following him Simpson, Schroeder, and others, put forward the "foreign body" theory, according to which, towards the end of pregnancy, due to phenomena of degeneration in the fetal membranes, a disruption of the (previously strong) connection of the fetal egg with the uterine walls occurs, and as a result of this, it becomes, as it were, a foreign body and therefore causes uterine contractions.
All these theories boil down in general to purely physico-mechanical moments, which, however, are nothing more than auxiliary factors, in themselves insufficient to cause childbirth under normal conditions.
In 1858, Brown-Séquard suggested that the onset of childbirth is caused by an overload of the mother's blood with CO2 (he injected CO2-rich dog blood into the aorta of pregnant rabbits and very soon after this observed childbirth; but these experiments are not convincing, since the injection of foreign blood is in itself too serious an intervention, fraught with all sorts of consequences).
Some authors saw the cause of the onset of childbirth in the fact that various chemical substances circulating in the pregnant woman's blood and necessary for the development of the fetus accumulate in excess by the end of pregnancy and therefore begin to act on the motor centers of the uterus (Spiegelberg).
Others spoke of a similar significance of products of regressive metamorphosis (Hasse).
Standing apart is the little-popular among obstetricians and poorly substantiated, purely speculative theory of the "cumulative action of cyclic phenomena"; it sees in the periods of pregnancy corresponding to the menstrual term, increased hyperemia and excitability of the uterus (more frequent bleeding and abortions at this time), increasing with each month more and more in connection with the non-appearing menstruation, as a result of which a cumulative action of some irritating substances occurs, accumulating as a result of the 10-fold absence of menstruation.
Of significant interest are various theories that draw an analogy between the processes of pregnancy and phenomena of immunity and see the cause of the onset of childbirth in the biochemical relationships between the mother and the fetus.
Their essence boils down to the following: the fetus produces substances which, entering the mother's blood, act like an antigen; therefore, the onset of childbirth is explained by processes similar to phenomena of immunity.
According to Veit, substances called syncytiotoxins are separated from the syncytial covering of the chorionic villi, to which the maternal organism reacts by the formation of antitoxins - syncytiolysins.
Towards the end of pregnancy, too much antigen is formed, and therefore neutralization turns out to be already insufficient, which is reflected both in the vasomotor apparatuses and in the organs of metabolism.
Schäffer believes that erythrocytes are carriers of toxic substances produced by the syncytium, in connection with which their resistance decreases significantly towards the end of pregnancy, and when this reaches an extreme degree, contractions of the uterine fundus occur.
A functionally complete syncytium initially rather increases even the resistance of erythrocytes; therefore, during pregnancy, there are no uterine contractions that could cause childbirth; towards the end of pregnancy, however, in connection with regressive changes in the syncytium, the resistance of erythrocytes falls and therefore childbirth occurs.
However, the theory of immunity can be accepted only with a certain caution, since there are still no precise proofs that the fetus produces substances acting like an antigen in the mother's organism.
However, interesting experiments by Sauerbruch and Heide apparently served as some support for the theory of immunity.
These experiments consisted in the artificial induction of parabiosis by surgically connecting a pregnant and a non-pregnant rat.
It turned out that before the onset of childbirth in the first, the second becomes ill, and the more severely, the less time has passed since the operation of connecting them both.
When connecting two females with different stages of pregnancy, in most cases, the one that is in the beginning of pregnancy has an abortion, and the other gives birth on time.
From this, Heyde concluded that the products of fetal metabolism (specifically protein ones) entering the mother's blood in large quantities at the end of pregnancy, acting as an antigen, mix with the antibodies formed under their influence in the maternal organism and together form an anaphylactic poison that triggers the onset of childbirth.
However, his experiments with injecting pregnant animals with fetal blood serum proved successful in only 1/4 of cases, i.e., they induced labor activity. Strictly speaking, even this is not very convincing, since Kurdinovsky's experiments proved that even neutral fluid injections (e.g., physiological NaCl solution) can, insofar as they are associated with pain, cause uterine contractions of a purely reflex nature. The view of childbirth as an anaphylactic phenomenon has by no means proven to be generally accepted. For example, Guggisberg, through his experimental research, precisely proved that anaphylactic phenomena are not observed during pregnancy. Esch reached the same conclusion; by injecting fetal serum into pregnant women, he became convinced of the non-specificity of the reaction obtained, if only because it was also observed in non-pregnant women. Therefore, the idea of the pregnant woman's serum having increased sensitivity to protein substances of fetal origin must be rejected, and consequently, childbirth is not an anaphylactic phenomenon. The production by the fetus of substances that cause childbirth cannot, of course, be completely denied, but they are by no means of an anaphylactic nature. Recently, in connection with the development of endocrinology, a tendency has appeared to treat the problem of the onset of childbirth in the light of the doctrine of internal secretion, all the more so because significant changes in many endocrine glands in connection with pregnancy have been precisely established. Since experimental studies (Kurdinovsky, 1903, and many others) established an extremely increased sensitivity of the uterus to adrenaline, which even in the smallest doses proved to be the strongest excitant of its contractions—which was also confirmed in clinical observations—many thought that the cause of the onset of childbirth is the accumulation of adrenaline in the blood at the end of pregnancy (hyperadrenalinemia), which sensitizes the uterus, gradually preparing it for labor activity. What has been said about adrenaline can to a large extent also be applied to pituitrin; its stimulating effect on uterine musculature has been precisely established both experimentally and clinically, and, among other things, was verified with a tocodynamometer in clinical experiments by Malinovsky. Although the presence of adrenaline and pituitrin in the blood of pregnant women, and specifically in increased quantities, has not yet been flawlessly proven by the research methods available to us now, this does not speak against the entirely possible role of these substances as powerful excitants of the contractile, or rather, labor activity of the uterus. Recently, Guggisberg and his students proved that similar substances stimulating the uterus are also found in the placenta; there are especially many of them in a mature placenta, whereas in an immature one, there are comparatively very few; these substances are of a specific nature, i.e., they are never observed in such large quantities in other organs. Finally, there is an indication that hormones are also produced in the thyroid gland that act on the uterus in an analogous manner (Guggisberg and others). All these diverse data, however, do not yet make it possible to prove with complete certainty to what extent the indicated hormones determine the onset of childbirth, although they undoubtedly must play a certain role as strong excitants of the motor function of the uterus. Despite the enormous amount of effort expended on resolving the question of the causes of the onset of childbirth, the long series of experimental studies, clinical observations, and all sorts of purely speculative constructs, and finally, later theories already solidly grounded in strictly scientific data, this extremely complex problem is still far from its final resolution.
E. Kurdinovsky. II. Clinical course of physiological childbirth. Childbirth in some cases, especially in primigravidae, begins with so-called premonitory pains, special contractions of the uterus (according to some authors, contractions only of the uterine fundus), which, unlike true labor pains, are not accompanied by dilation of the cervix and

Figure 2.
Figure 3.
Figure 2. Cervix of a primipara at the beginning of labor. Figure 3. Primipara. Dilation stage. The upper part of the cervical canal is effaced by the insertion of the amniotic sac. Premonitory contractions are weaker than true ones, are accompanied by pulling pains in the lower back and sacrum, but do not have a regular rhythm. Following the premonitory signs, and sometimes without them, true labor contractions develop, i.e., childbirth begins. The act of childbirth sequentially breaks down into three stages: 1) the stage of dilation (preparation of the soft birth canal for the passage of the fetus), 2) the stage of expulsion (expulsion of the fetus through the dilated birth canal), and 3) the placental stage (separation and expulsion of the placenta). Clini-

Figure 4.
Figure 5.
Figure 4. Primipara. The cervix is fully effaced. The external os is still closed ("obstetric os"). Figure 5. Primipara. The cervix is effaced, the external os is smoothed out, presenting only a narrow rim. The stage of dilation is finished. cally objective signs of the onset of labor activity serve as: a) true labor contractions—regular, periodically repeating contractions of the uterus, b) discharge of mucus stained with blood ("es zeichnet" of the Germans, "labor is marked"), c) dilation and effacement of the uterine os, d) in some cases, discharge of amniotic fluid, and finally e) in the absence of the amniotic sac, the formation of a caput succedaneum. In the stage of dilation, the unfolding and effacement of the uterine cervix occurs from its internal os to the external one. This is facilitated, on the one hand, by the stretching (distraction) of the muscle fibers of the cervix, occurring under the influence of the contraction of the uterine body (contractions), and on the other hand, by the action of the amniotic sac, i.e., that portion of the fetal membranes which, together with the forewaters, bulges into the region of the internal os. In primiparae, the unfolding of the cervical canal occurs from top to bottom: first
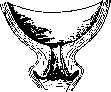
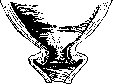
Figure 6.
Figure 7.
Figure 6. Multipara. Beginning of dilation. Figure 7. Multipara. Effacement of the upper half of the cervix and simultaneous opening of the external os. the internal os opens, then the cervical canal, and in conclusion, the external os. The external os (in primiparae) with an effaced cervix is called the "obstetric os." In multiparae, the effacement of the cervix and the dilation of the external os occur simultaneously (Figs. 2-8). In the stage of dilation, the presenting part (the head) as a rule does not make forward progressive movements. It is located entirely above the pelvic inlet (it can be felt from above over the pubic symphysis) or only enters it with a certain segment. During an internal examination, the degree of dilation of the uterine os (the stages of the labor act in the dilation period) is determined and denoted by the number of fingers that can be freely inserted into the os (opening of 1-2-3-4 fingers, full opening, or the edges of the os are not palpable). Without resorting to an internal examination, one can be guided in deciding the degree of dilation by the character, frequency, and strength of the labor contractions: weak, short contractions appearing every 10-15 minutes indicate the beginning of the dilation stage; strong, prolonged ones with intervals of 2-3 minutes will rather indicate the end of the dilation stage. Unterberger proposed judging the degree of dilation of the uterine os by the so-called boundary (contraction) ring, palpable, especially in primiparae, through the abdominal walls. During contractions, one can palpate, and in some cases even see with the eye, a protruding groove directly under the edge of the contracting uterine body (hollow muscle), which corresponds to the contraction ring. If the latter is located three transverse fingers above the symphysis, then, according to Unterberger, the os is dilated by three fingers. When the contraction ring is 6 cm above the pubis, the os can be considered fully dilated. The end of the dilation stage is determined by the moment of full dilation of the uterine os, approximately to a size of 10 cm, when there is already
Figure 8. Multipara. The cervical canal is unfolded, the external os is effaced to the size of a narrow rim. End of the dilation stage.
the possibility of the head of a full-term fetus passing through. Under normal conditions, the end of the dilation period usually coincides with the moment of rupture of the fetal membranes and the outflow of the forewaters, but this is observed far from always (in approximately 55% of cases): the fetal membrane may rupture before and after the end of the dilation period (premature, early rupture of the membrane and delayed rupture-birth of the child in the fetal membrane, "in a caul"). If the membrane ruptures too early, childbirth has a prolonged course ("dry labor"). Delayed rupture of the fetal membranes may lead to premature separation of the placenta and death of the fetus from asphyxia. The duration of the dilation period varies with different positions and presentations of the fetus. It also depends on the strength and frequency of uterine contractions. With normal occipital presentation, the average duration of the first stage of labor is calculated for primiparas as 16-18 hours, and for multiparas as 10-12 hours. Complete dilation of the uterine cervix, i.e., the beginning of the expulsion period, is clinically marked by the onset of bearing down, i.e., the contraction of the striated musculature of the abdominal press. Thanks to bearing down, the expulsive forces of labor increase almost twofold (Schatz). In this period, the head, resp. the presenting part, makes a series of progressive movements along the axis of the pelvis (translation according to Selheim) and a series of additional movements-rotational movements around the longitudinal axis of the body and movements around the frontal axis (see below). The action of bearing down consists in the fact that the parturient, holding her breath during a contraction (as during defecation), activates the abdominal press and thereby, by increasing the intra-abdominal pressure, assists the progressive movement of the fetus forward. During the expulsion period, under the action of contractions and bearing down, the head enters the pelvis first with the smallest segment. Its greatest circumference is still above the pelvic inlet, the head is mobile or slightly fixed, on internal examination linea terminalis, s. innominata is not entirely free, as a certain segment (pole) of the head has already entered the pelvic inlet, but the promontory is still accessible to the examining finger, the sagittal suture is closer to the transverse diameter of the pelvis. Then the head enters the pelvis with the largest segment. Above the pelvic inlet, a certain pole of the head can still be palpated, it covers only a small part of the symphysis and sacrum; on internal examination, without pushing the head away, the promontory can no longer be reached, the sagittal suture is slightly in an oblique diameter, the sacral hollow is free. Further, the head enters the cavity of the pelvis. Above it, it is not determined, on internal examination the sagittal suture is in one of the oblique diameters, the sacral hollow is completely filled, spina ischii is not determined. The head reaches the pelvic floor. This is indicated by: the gaping anal opening, the sensation in the parturient of an urge to the low part, the passage of feces, and sometimes also cramps in the calf muscles. The head is at the pelvic outlet. In the gaping vulvar ring, a small segment of the presenting part becomes visible, appearing during a contraction-bearing down and hiding again during a pause ("crowning" of the head). Following crowning comes "crowning": the crowning head, advancing more and more forward, during a pause no longer retreats back, the vulva remains gaping. Contractions and bearing down during "crowning" and "crowning" reach maximum tension ("shaking" bearing down). The crowning of the head and its birth is accompanied by circular stretching of the vulvar ring. Following the birth of the head, the birth of the body quickly follows. The born head turns with its face, depending on the position, to one or the other thigh of the mother (in the first position-to the right, in the second-to the left). The birth of the shoulders occurs by the same mechanism as the birth of the head. The crowning of the shoulder girdle produces no greater stretching of the vulvar ring than the head does. This circumstance is important to consider when protecting the perineum (see below). With the birth of the fetus, the expulsion period ends and the placental period begins. The expulsion period lasts on average for primiparas 2-3 hours, for multiparas-half an hour to an hour. The placental period is the shortest (15-20 min.), but at the same time the most dangerous and responsible period of the act of labor. In it, it is difficult to distinguish: the moment of separation of the placenta from the walls of the uterus and the moment of its expulsion from the birth canal. Normally, separation of the placenta occurs after the birth of the child. Separation of the placenta before the birth of the fetus is a very serious complication, which leads to the death of the fetus and can have the most fatal consequences for the mother (see Placenta, premature separation of the placenta). Separation of the placenta occurs due to contractions of the uterus ("placental" contractions). Separation occurs at the border of the compact and spongy layers of the shedding membrane, it does not occur immediately and not in the same way. A distinction is made between separation of the placenta according to Duncan (the placenta separates laterally, goes forward with one of its edges and only then with its maternal side, the membranes together with the umbilical cord retain their position on the amniotic side of the placenta), according to Schultze (first the central part of the placenta separates with the formation of the so-called retroplacental hematoma-a collection of blood between the placenta and the uterine wall-the placenta exits with the amniotic, resp. fetal side, forward goes the central part of the placenta together with the umbilical cord, the membranes turn inside out, covering the maternal surface of the placenta) and according to Franz
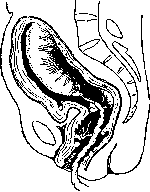
Figure 9. Beginning separation of the placenta (Duncan's method).

Figure 10. Exit of the placenta through the vagina with the lower edge forward (Duncan's method). (separation of the entire surface of the placenta simultaneously) (figs. 9-12). The obstetrician must know well and clearly the clinical picture of the course of the placental period, as complications often occur here requiring medical intervention. It is especially important to know the clinical signs of a separated placenta. The most important of them are: 1) Schröder's sign (occurs in 95-97%)-the fundus of the uterus rises above the navel, usually to the right, the uterus becomes narrower and flatter (the anteroposterior diameter decreases); 2) Alfeld's sign-lengthening of the external segment of the umbilical cord (a clamp placed on the umbilical cord moves away from the vulva by 10-12 cm); 3) Küstner's sign (95-98%)-when pressing with a hand above the symphysis, the external segment of the umbilical cord in an unseparated placenta goes back into the vagina and remains in place if the placenta has separated from the uterine wall; 4) the appearance of a bulging above the pubis: the anterior wall of the lower segment, into which the separated placenta descends, bulges forward under the pressure of the latter, lifting the abdominal wall forward; between this bulge and the hollow muscle (upper segment) a distinctly expressed groove can sometimes be traced (a kind of "retraction" or "contraction" ring); 5) the sign
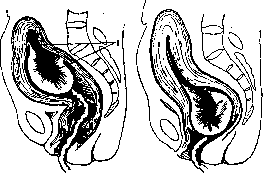
Fig. 11. Central separation of the placenta (Schultze's method) 1 - retroplacental hemorrhage.
Figure 12. The placenta has been expelled from the uterine cavity and is in the cervix in a folded state (Schultze's method). Strassmann's method - light tapping with the fingertips in the area of the uterine fundus with an unseparated placenta is felt as a slight wave (blood in the umbilical vein is in contact with the mother's blood), under opposite conditions this wave is absent; with more energetic pressure on the uterine fundus, along with a slight wave, tension of the umbilical vein with its twisting (overfilling with blood) into a spiral can be obtained (Hochenbichler's sign); b) Klein's sign - when the woman strains or pressure is applied to the uterus, the umbilical cord protruding from the vulva is pulled out and in case of placental separation it does not retract back; c) Mikulicz-Radecki and Calmann's sign - the sensation of a urge to the low that women complain of, due to pressure from the descending placenta on the rectum. The expulsion of the separated placenta occurs either spontaneously (contractions and bearing down) or with the use of obstetric aids (see Obstetric manual maneuvers). In the placental period, the woman loses a certain amount of blood. When the placenta separates according to Duncan's method (from the edge), bleeding may be observed throughout the placental period, while with Schultze's method, the retroplacental hematoma empties after complete separation and expulsion of the placenta. Blood loss varies within 200-600 cm3 (see Postpartum period, postpartum hemorrhages). Bleeding after the birth of the placenta - stops due to 1) contractions of the uterus (the lumen of the torn vessels decreases), 2) the formation of clots in the vessels (especially in the atonic state of the uterine musculature) and 3) the twisting of the thin-walled partitions in which the vessels pass. The average duration of the placental period does not exceed 30 minutes in normal conditions. According to Varnegros (radiograms), the placenta separates from the uterine walls 5 minutes after the birth of the child. Weibel on his X-ray films only in 1/3 of cases found the placenta separated at this time, in 2/3 of cases it still remained in situ. According to Stöckel, final separation of the placenta occurs in the first quarter hour. In any case, within the first half hour after the birth of the child, the placenta in normal conditions is always separated from the uterine walls. Expulsion of the placenta occurs in 70% of cases within 11/2 hours after the birth of the child, in 20% - within the first hour, in 10% separation and expulsion of the placenta continues for more than an hour. Variations (deviations) of the main normal mechanism. Occipital presentations (flexion type). Occipital presentation with the anterior position (occiput and back facing forward) is the only one when the mechanism of childbirth and its clinical course should be considered normal, physiological. But even with this main normal mechanism, deviations (variations) are observed that have great practical importance. 1. Childbirth with the occiput and back facing backward (occurring in approximately 1% of all cephalic presentations). There are two varieties of such childbirths: a) posterior position of occipital presentation and b) anterior-head (anterior-cranial) presentation. The essence of these two variants is that the back of the fetus, sometimes during pregnancy, but more often during childbirth, turns backward (incorrect rotation of the occiput). With the development of labor, the position can correct itself: often the head makes a strong turn, and the occiput together with the back turns forward. In the etiology of stationary (remaining throughout the entire process of labor) anterior-head presentation and posterior position of occipital presentation, the decisive role is played by: the condition of the soft birth passages, resp. the pelvic floor, pelvic anomalies (change in shape and size), as well as the shape and size of the head (small head). Among the predisposing (stimulating) factors, one can note premature rupture of membranes, polyhydramnios, pendulous abdomen, cord entanglement, etc. The clinical course of childbirth with posterior position of occipital presentation in the dilatation period is usual (as with the anterior position). The difference begins with the expulsion period. Here the mechanism of childbirth proceeds in a peculiar way. First, the head performs strong flexion due to the descent of the small fontanelle, which at first plays the role of the guiding point (see below - mechanism of labor). At the second moment of the mechanism (rotation), the occiput turns backward, toward the sacral cavity, and the area of the large fontanelle approaches the symphysis pubis. In this case, if speaking precisely, the point between the large and small fontanelles should be considered the guiding point. For purely practical considerations, with posterior position of occipital presentation, the large fontanelle can be conditionally considered the guiding point. During crowning, the head, being born in posterior position of occipital presentation, has two points of fixation (two hypomochlia) - one to enhance flexion and another to deflex (for extension). At the vulvar ring, the head, as with the anterior position, engages with the small fontanelle. Reaching the pubic arch, it is fixed here by its anterior edge in the area of the hairy part of the head (first hypomochlion), flexion occurs, thanks to which the occiput rolls over the perineum to the suboccipital region. Then the suboccipital fossa is fixed in the area of the coccyx (second hypomochlion), the head extends, freeing the forehead, face, and chin from under the pubic arch. Thus, in general, the mechanism of childbirth with posterior position of occipital presentation consists of: 1) flexion (when the head enters the pelvis), 2) incorrect rotation in the pelvis (the small fontanelle is directed backward) and 3) additional flexion and extension (during crowning). The presenting circumference of the head is planum suboccipito-frontale (33 cm), corresponding to the average oblique diameter. The configuration of the head with posterior position of occipital presentation is dolichocephalic, with a sharp depression in the area of the large fontanelle. The birth tumor is located on the presenting parietal bone, closer to the large fontanelle. The configuration of the head here occurs extremely slowly, with a huge expenditure of labor forces. Very often, after the head has passed the pelvic plane, its forward movement stops. Anterior-head presentation, externally resembling posterior position of occipital presentation, differs from it in principle in that the head here is not flexed, but on the contrary, is in a slight degree of extension (the chin somewhat retracts from the chest). Anterior-head presentation occurs as a transient (temporary) condition in flat pelvises (see Narrow pelvis). In it, the back and occiput, as well as with posterior position of occipital presentation, are directed backward. The head, performing its mechanism, enters the pelvis with the sagittal suture in the transverse diameter (partially in the oblique). Due to the extension of the head, the large fontanelle stands in the same horizontal plane with the small one or even slightly below it. During rotation, the anterior part of the parietal bone (area of the large fontanelle) turns forward, at the same time descending lower. The head passes through the pelvic cavity, entering one of its oblique diameters, and rotates with the occiput backward. The mechanism of crowning proceeds according to the type of posterior position of occipital presentation, only the guiding point, points of fixation, the presenting circumference through the vulvar ring and the configuration of the head will be different. During engagement in the vulva, the large fontanelle and forehead appear first. Gradually crowning, the head moves forward until the glabella approaches the pubic arch. Fixed in this way, the head performs flexion, during which the occiput to the suboccipital tubercle emerges through the perineum. Fixed last in the area of the coccyx, the head extends, freeing the face and chin from under the symphysis. Thus, with anterior-head presentation we have: 1) slight extension when the head enters the pelvis (descent of the large fontanelle), 2) incorrect rotation of the head (with the occiput backward), 3) flexion and 4) extension of the head. The guiding point - undoubtedly the large fontanelle. Two points of fixation (two hypomochlia): 1) glabella and 2) occipital tubercle. The presenting circumference of the head - planum fronto-occipitale (34 cm), corresponding to the direct diameter of the head. The configuration of the head - brachycephalic (tower shape). The head tumor is located in the area of the large fontanelle on the presenting parietal bone. Bumm considers anterior-head presentation as the initial stage of face presentation, i.e. he attributes it not to the flexion, but to the extension type of the mechanism of labor. Timely recognition of the described variant of the main occipital mechanism does not always succeed. More often such recognition is made only at the moment of crowning. In diagnosis, one must first of all keep in mind that one can speak of posterior position of occipital presentation and anterior-head presentation only when the head is already on the pelvic floor, while it is at the entrance to the pelvis or in the wide part of the pelvic cavity, correction of the presentation is always possible.
During internal examination, main attention should be fixed on the position of the fontanelles (fig. 13 and 14). In the posterior view of occipital presentation (under the pubic area the region of the large fontanelle), the small fontanelle (posteriorly) is low-lying,
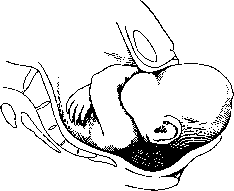
Figure 13. Crown presentation in posterior occipital presentation. The head is in maximum flexion, with the occiput in the genital fissure, the region of the large fontanelle under the pubic symphysis. As soon as the frontal eminences pass the edge of the pubic arch, extension of the head occurs, thanks to which the occiput quickly appears one after another over the perineum, while the face is under the pubic arch.
the large fontanelle is higher (anteriorly), sometimes difficult to reach, the anterior angle of it clearly lies higher than the posterior, there is marked flexion of the head. In anterior-occipital presentation under the pubic area the large fontanelle is also determined, and all its angles lie in one horizontal plane, sometimes the frontal suture can be traced quite far; on the other side (posteriorly) one can always reach (sometimes with difficulty) the small fontanelle. Prognosis. Childbirth with the spine and with the occiput turned backward usually ends spontaneously. There are still some moments which cloud the prediction. First of all, it should be noted that the prognosis for the mother and child in anterior-occipital presentation, all other conditions being equal, is worse than in the posterior view of occipital presentation. Mortality of children due to asphyxia in anterior-occipital presentation is three times greater than in the anterior view of occipital presentation. The expulsion period is significantly prolonged. If, in addition, there is a narrowed or narrow pelvis, which is not infrequently observed, or unyielding soft parts, the prognosis understandably worsens significantly for both the parturient and the fetus. Often there is entrapment of the anterior lip of the cervix and its edema (engagement of the head by its large circumference). Due to great resistance, contractions often are unproductive. As a result, secondary weakness of labor pains often occurs. In addition, in
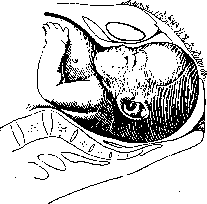
Figure 14. Engagement of the head in anterior-occipital presentation.
Childbirth with the occiput backward presents great difficulties in crown presentation (under the pubic arch the head must perform strong flexion). As a result, there is always great danger of damage to the perineum and even tearing of the m. levatoris. Management of childbirth should be strictly expectant. Protection of the perineum is carried out according to general rules (see below - management of childbirth). One should only remember that according to the mechanism, flexion of the head here should be done not toward the perineum, as in the anterior view of occipital presentation, but toward the symphysis. In the presence of appropriate indications (fetal asphyxia, rigidity of tissues, etc.) one has to resort to one or another operative intervention. The described variant of the flexion mechanism of childbirth more often requires and operation of applying forceps (according to Hogler in 14%). When applying forceps, one should remember that traction here should never be done downward (backward): unfavorable extension (see Obstetric forceps). 2. The second variant of the basic mechanism in occipital presentations - medium and low, resp. deep, transverse position of the sagittal suture. In this anomaly, for one reason or another, the head does not perform the second moment of the mechanism (rotation), positioning itself with its sagittal suture in the transverse dimension of the pelvic cavity (medium transverse position of the head) or even in the pelvic outlet (low, resp. deep, transverse position of the head). There is also a high transverse position of the head (prolonged standing of the sagittal suture in the transverse dimension of the pelvic inlet); it is observed in a flat pelvis as one of the moments of the mechanism of childbirth in the period of head configuration
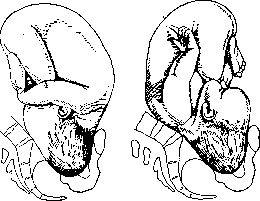
Figure 15. Positio occipitopubica.
Figure 16. Positio occipitosacralis. (see Narrow pelvis).-Transverse position of the head, low and medium, most often occurs in the so-called Deventer pelvis (simple flat pelvis - see Narrow pelvis). In all cases, during the expulsion period, with good contractions and a head low-lying in the pelvis, if childbirth does not progress forward, one should think, along with the possibility of narrowing of the pelvic outlet and the presence of the posterior view of occipital presentation, resp. anterior-occipital presentation, also about low or medium transverse position of the head. During internal examination, the head is usually on the pelvic floor, the sagittal suture is in the transverse dimension, the small fontanelle lies on one side, the large one on the other. The large fontanelle often stands at the same level as the small one (insufficient flexion of the head).-Childbirth in medium and low (deep) transverse position of the head rarely end naturally. They are prolonged, the fetus is threatened with asphyxia, which is why one often has to resort to artificial delivery. In such cases, forceps are usually applied. Before applying forceps, it is recommended for the parturient to lie on the side toward which the small fontanelle is looking, as in this variant it should be considered the guiding point. In general, in managing childbirth in the described anomaly of the mechanism, they should be managed according to the type of normal occipital presentation. 3. High direct position of the head (insertion of the head in the direct dimension of the pelvis) - a rarely occurring variant of the normal mechanism, in which the head at the pelvic inlet is established with its sagittal suture in the direct dimension corresponding to the true conjugate. The head can be inserted in such a way that its occiput is turned toward the pubis - positio occipitopubica (fig. 15) (it occurs more often and mainly in multiparas); the opposite insertion - positio occipitosacralis (fig. 16), when the occiput is turned
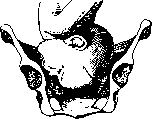
Figure 17. Beginning extension, frontal insertion at the onset of labor in face presentation.

Figure 18. Descent of the chin during labor in face presentation.
backward (toward the sacral promontory), is observed extremely rarely, and almost always in primiparas. The etiology of high direct insertion of the head remains unexplained to this day. Most obstetricians see the cause of this anomaly in changes in the shape and size of the pelvis (a greatly narrowed pelvis has a great influence). Direct insertion of the head before labor, sub graviditate (primary), is hardly encountered (the only, and that doubtful case belongs to Glocker), it more often occurs already during labor. In positio occipitopubica (anterior insertion) childbirth can end spontaneously, but in protracted cases one has to resort to forceps. Initially, in the absence of threatening phenomena, one can try Walcher's position (see Walcher's hanging position). With a movable head, one should perform rotation and extraction, but with an inserted head - apply forceps. In posterior direct insertion of the head, childbirth almost always has to be ended by operative means (rotation, forceps, perforation, cesarean section). Henkel for this rare anomaly of head insertion recommended manual correction (under anesthesia): with the help of 4 fingers of the hand introduced into the uterine cavity, placed Fig.19. Face presentation, posteriorly of the head, extension is completed, the chin is to the right and anteriorly should turn only 45°, to approach under the pubic arch.
and the large one - to the right and backward. 4. Excessive rotation of the shoulders - the shoulders pass through the pelvic cavity by the same oblique dimension as the sagittal suture (normally they pass in the opposite oblique). This anomaly has no practical significance. Extension (deflexion, facial) type of the mechanism of childbirth. The antithesis of the mechanism of childbirth in the anterior view of occipital presentation is face presentation, in which the head, being in a state of maximum extension, passes through the pelvis by the other pole of its ellipsoid - with the chin forward. Extension (extensio, defleXio) in this presentation is so marked that the occiput of the fetus lies on the shoulder girdle. Face presentations occur

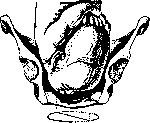
Figure 20. Face presentation, extension completed, the chin is to the right and posteriorly should turn 135°, to approach under the pubic arch.
approximately in 1:200 births (0.52% according to Demuth). Extremely rarely, as an exception, the head is established in face presentation during pregnancy (primary face presentation), much more often, as a rule, such presentation arises during labor (secondary face presentation). In the origin of face presentations, numerous and heterogeneous etiological factors play a role. Winkel collected up to 33 hypotheses on the question of the etiology of the presentation under discussion. All of them, however, do not withstand strict criticism. Among the factors that may play a role in the etiology of face presentations, usually noted are: narrow pelvis, which, according to Demuth, occurs in 44.6% (Leopold's triad: narrow pelvis, primipara, face presentation), one or another abnormal shape of the head, oblique position of the uterus, unyielding lower segment of the uterus (Bumm), tumors of the neck (hygroma), congenital goiter in the fetus
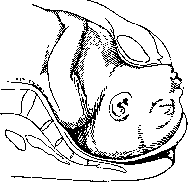
Figure 21. Engagement of the face.
etc. Kernauner sees the cause of the extension type mechanism of Childbirth in a violation of the function of the atlanto-occipital joint. Face presentations, upon external and internal examination, present a completely different picture compared to occipital presentations (fig. 17-24). The diagnostic points for face presentation are given in the accompanying table. Some (Fenomenov, Malinovsky) suggest determining the position in face presentations not by the spine, but by

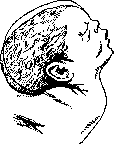
Figure 23. Configuration of the head in face presentation.
Fetus and its parts First position External examination Head and spine Buttocks and small parts Heartbeat Facial line Chin Forehead Presents Shoulders External rotation Birth tumor Left occiput, forms a sharp angle with the spine Lie together on the same side where the heartbeat is heard To the right of the midline under the navel (on the chest side) Internal examination In the transverse diameter, synclitically or in a slight Naegele's inclination To the left To the right Right half of the face In the left oblique diameter of the pelvis To the mother's right thigh More on the right half of the face In face presentation, the same positions and types are distinguished as in cephalic presentations Figure 22. Emergence of the head in face presentation. to the chin (chin forward-anterior view and vice versa). In internal examination, one can only speak of face presentation if the examining finger reaches the tip of the nose, and with further advancement-the chin, with one side of the face being accessible to palpation, and on the other only the forehead. It should be borne in mind that internal examination gives a clear picture only shortly after the rupture of the fetal membranes, before the birth tumor has had time to form. In cases of long-standing head engagement, with long-ago ruptured waters, recognition of face presentation becomes difficult, as on the face, due to the birth tumor, all its irregularities are smoothed out, the cheeks and lips become edematous (only the nose retains __________________. its characteristic shape), the depression of the mouth upon palpation resembles the anus. Face presentation in this case can be mistaken for a pure breech presentation. For recognition, it is recommended to carefully introduce a finger into the existing depression on the presenting part. If it is the mouth, one can feel the jaws, tongue, one can catch sucking movements of the fetus; in breech presentation, this data is not available, and in addition, the extracted finger is found to be stained with meconium, which does not happen in face presentation. Once again, it should be emphasized that internal examination in face presentations should be performed with extreme caution Second position Right occiput, forms a sharp angle with the spine Lie together on the same side where the heartbeat is heard To the left of the midline under the navel (on the chest side) In the transverse diameter, synclitically or in a slight Naegele's inclination To the right To the left Left half of the face In the right oblique To the left thigh More on the left half of the face (one can easily damage such delicate organs as the eyes), aseptically, necessarily with the pulp of the finger, avoiding contact with the nail. One should also refrain from introducing a finger into the mouth of the fetus (one can cause premature respiratory movements). Course of Childbirth in face presentation. The dilatation period proceeds the same as in other head presentations. With its completion, the head enters the pelvis
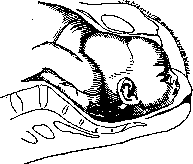
Figure 24. Face presentation. Abnormal backward rotation of the chin. Arrest of labor.
the so-called facial line (analogous to the sagittal suture), running from the frontal suture along the bridge of the nose to the chin. This line stands in the transverse diameter of the pelvis, and in this position the head, without making a screw-like movement, reaches the pelvic floor and only here begins rotation with the chin anteriorly. The mechanism of the face emerging through the vulvar ring is as follows. The chin emerges first under the symphysis. Emerging further, the face reaches the pubic arch with the sublingual region. The sublingual region takes on the role of the hypomochlion. Fixing itself in the region of the hyoid bone, the head performs flexion, during which the forehead, and the anterior and posterior parts of the head, roll over the perineum. Thus, the entire mechanism of childbirth in face presentation consists of three moments: 1) extension of the head (deflexion), which occurs throughout the entire distance from the inlet to the pelvic floor, 2) correct rotation with the chin anteriorly (at the pelvic floor), and 3) flexion (during emergence through the vulvar ring). The leading point is the chin. The point of fixation is the region of the hyoid bone; the emerging circumference—planum trachelo-bregmaticum (34 cm)—corresponds to the vertical diameter; the caput succedaneum is on one of the halves of the face (a terribly disfigured appearance); the configuration of the head is sharp dolichocephaly. Unlike occipital presentation (in which the head also has a dolichocephalic shape), the configured head in face presentations has a disfigured half of the face (caput succedaneum), and in addition, due to habit, the characteristic extension persists for 4-5 days. Edema on the face also lasts for 4-5 days. The management of labor in face presentation should be strictly expectant with extremely careful observation of the mechanism of labor. About 95% (according to Demelin) of births with this presentation end spontaneously. In view of this, at the present time, most obstetricians do not perform correction of face presentation into occipital, as was once proposed by Baudelocque, Thorn, Schatz, and others. The conversion of face presentation into cranial, according to Baudelocque, is performed by internal maneuvers: they enter the vagina with the entire hand, located opposite the occiput, grasp the latter, and directly pull it downward. Schatz proposed for the same purpose an external manual maneuver, the essence of which consists in the fact that by external maneuvers they try to convert the S-shaped curvature of the spine (face presentation) into a C-shaped one (cranial presentation). Correction of face presentation, according to Thorn (combined maneuver), is done in such a way that the internal hand, inserted into the uterus, tries to flex the head, the external one presses on the chest of the fetus in a posterior direction, and the assistant's hand, placed on the breech end of the fetus, facilitates the flexion of the trunk.
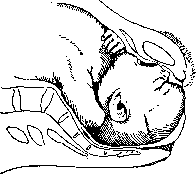
In face presentation, premature rupture of the fetal membranes is often observed (in 41% according to Demelin). Protection of the perineum requires especially careful attention, although it is carried out in the same way as in occipital presentations. It is often necessary to resort to perineotomy (see). Tears of the soft parts in face presentations occur in 28.6% (Masticy). One should carefully monitor the child's heartbeat (frequent asphyxia). Operative assistance is indicated in the same cases as in occipital presentation. The application of forceps sharply increases the danger of tears (avulsions of the m. levator ani). (Regarding the peculiarities of applying forceps, see Obstetric forceps.) Prognosis. Maternal mortality in face presentations is twice as high as in occipital (3%); infant mortality is three times higher (13-15% according to Winckel and 21.4% according to Demelin). Variants of the basic extension type of labor mechanism. 1. The so-called posterior variety of face presentation. Normal rotation in face presentation occurs at the pelvic floor, and in such a way that the chin rotates anteriorly (toward the pubis), and the forehead posteriorly. Only with such rotation are spontaneous births possible with the extension type of mechanism. But sometimes rotation goes in the opposite direction: the chin rotates posteriorly, and the forehead anteriorly. Under such conditions, childbirth is completely impossible for purely mechanical reasons. The posterior part of the head must pass through the pelvic ring together with the shoulders, and no matter how wide the pelvis is and no matter how small the head is, childbirth under these conditions is still impossible (the distance between the sternal notch and the small fontanelle is at least 13.4 cm). One cannot think about changing the position of the head when the face is impacted in the pelvis. Forceps also cannot be applied; even an attempt to apply forceps (Runge) should be considered a mistake. Only perforation of the fetal head or a cesarean section is possible, if there are no contraindications to them and if the mother wishes to have the child and the child is alive. 2. High straight engagement—and medium, resp. low (deep), standing of the head in face presentations are analogous in both course and assistance to the same anomalies in the flexion type of mechanism. 3. Brow presentation is a rather rare phenomenon (0.06-0.1% of all births). The mechanism of labor in it is far from being fully clarified. One can speak of brow presentation in the case where, upon internal examination, the forehead and parts of the face are felt: on one side one can reach the root of the nose, and on the other reach the anterior angle of the large fontanelle. Among the various etiological factors contributing to the occurrence of brow presentations, one of the most important is pelvic contraction. The head usually enters the pelvis with the frontal suture in the transverse diameter. It maintains this engagement throughout its entire progression to the pelvic floor. Here, rotation occurs with the occiput posteriorly, and the orbital region anteriorly. The mechanism of emergence in brow presentations occurs in such a way that with
Figure 25. Engagement of the head in brow presentation. The head and the position of the hand are drawn from nature.

the frontal suture standing in the direct diameter of the pelvic outlet, some point between the bridge of the nose and the chin (more often the upper jaw) is fixed under the pubic arch and the entire head rolls over the perineum around it. Thus, in general, the mechanism of childbirth in brow presentations can be characterized by the following moments: 1) slight flexion (medium degree of extension) of the head, 2) rotation with the orbital region anteriorly, 3) slight flexion, and 4) final very slight extension (during the emergence of the chin). The leading point is the root of the nose. The hypomochlion is the upper jaw. The emerging circumference
Figure 26. Emergence of the head in brow presentation.

of the head is planum maxillo-parietale (35 cm). The configuration of the head is triangular (with the apex at the forehead). The prognosis in brow presentations is doubtful. Maternal mortality is 5-10%, infant mortality is 30-50%. Births in brow presentation proceed with great complications (perineal tears, avulsions of the mm. levatores, vesicovaginal fistulas, uterine ruptures, fetal asphyxia, etc.); it is often necessary to resort to operative intervention, in particular to embryotomy operations. Extreme caution must be exercised with forceps. Under appropriate conditions, it is better to perform a version to the foot. Conversely, in a fixed brow presentation, it is better (especially for a novice obstetrician) not to use any corrective operations (Solovyov's proposal to convert brow presentations into face presentations by extending the head with a finger inserted into the mouth, and Kholmogorov's—to correct into occipital by flexing the head). Rarely, brow presentation is observed with the orbital region facing posteriorly. These cases were encountered in births with small (premature) fetuses. With a full-term fetus, births in the posterior variety of brow presentation (orbital region posteriorly) are impossible (perforation or cesarean section) (Figs. 25-27). Breech presentations. They occur on average in 3.5% of the total number of births. They are divided into breech presentations (flexion type) and footling presentations (extension type). Breech presentations, in turn, are divided into frank (only the buttocks present) and complete (the buttocks present together with the feet). Footling presentations are divided into complete (both feet present) and incomplete (one foot presents, usually the anterior one) (Figs. 28-30). Footling presentations occur in 33% of all breech presentations. Knee presentations are very rare. The reason why the fetus presents with its breech instead of the head
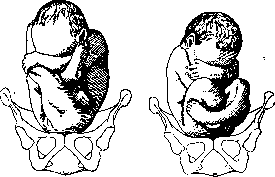
Figure 27. Configuration of the head in brow presentation.
Figure 28. Incomplete breech presentation. Figure 29. Complete breech presentation. Figure 30. Incomplete footling presentation. The anterior leg is flexed upward.
Related articles
Cite this page
“Childbirth.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/childbirth/